The risk is set
before labour begins.
The problem in brief
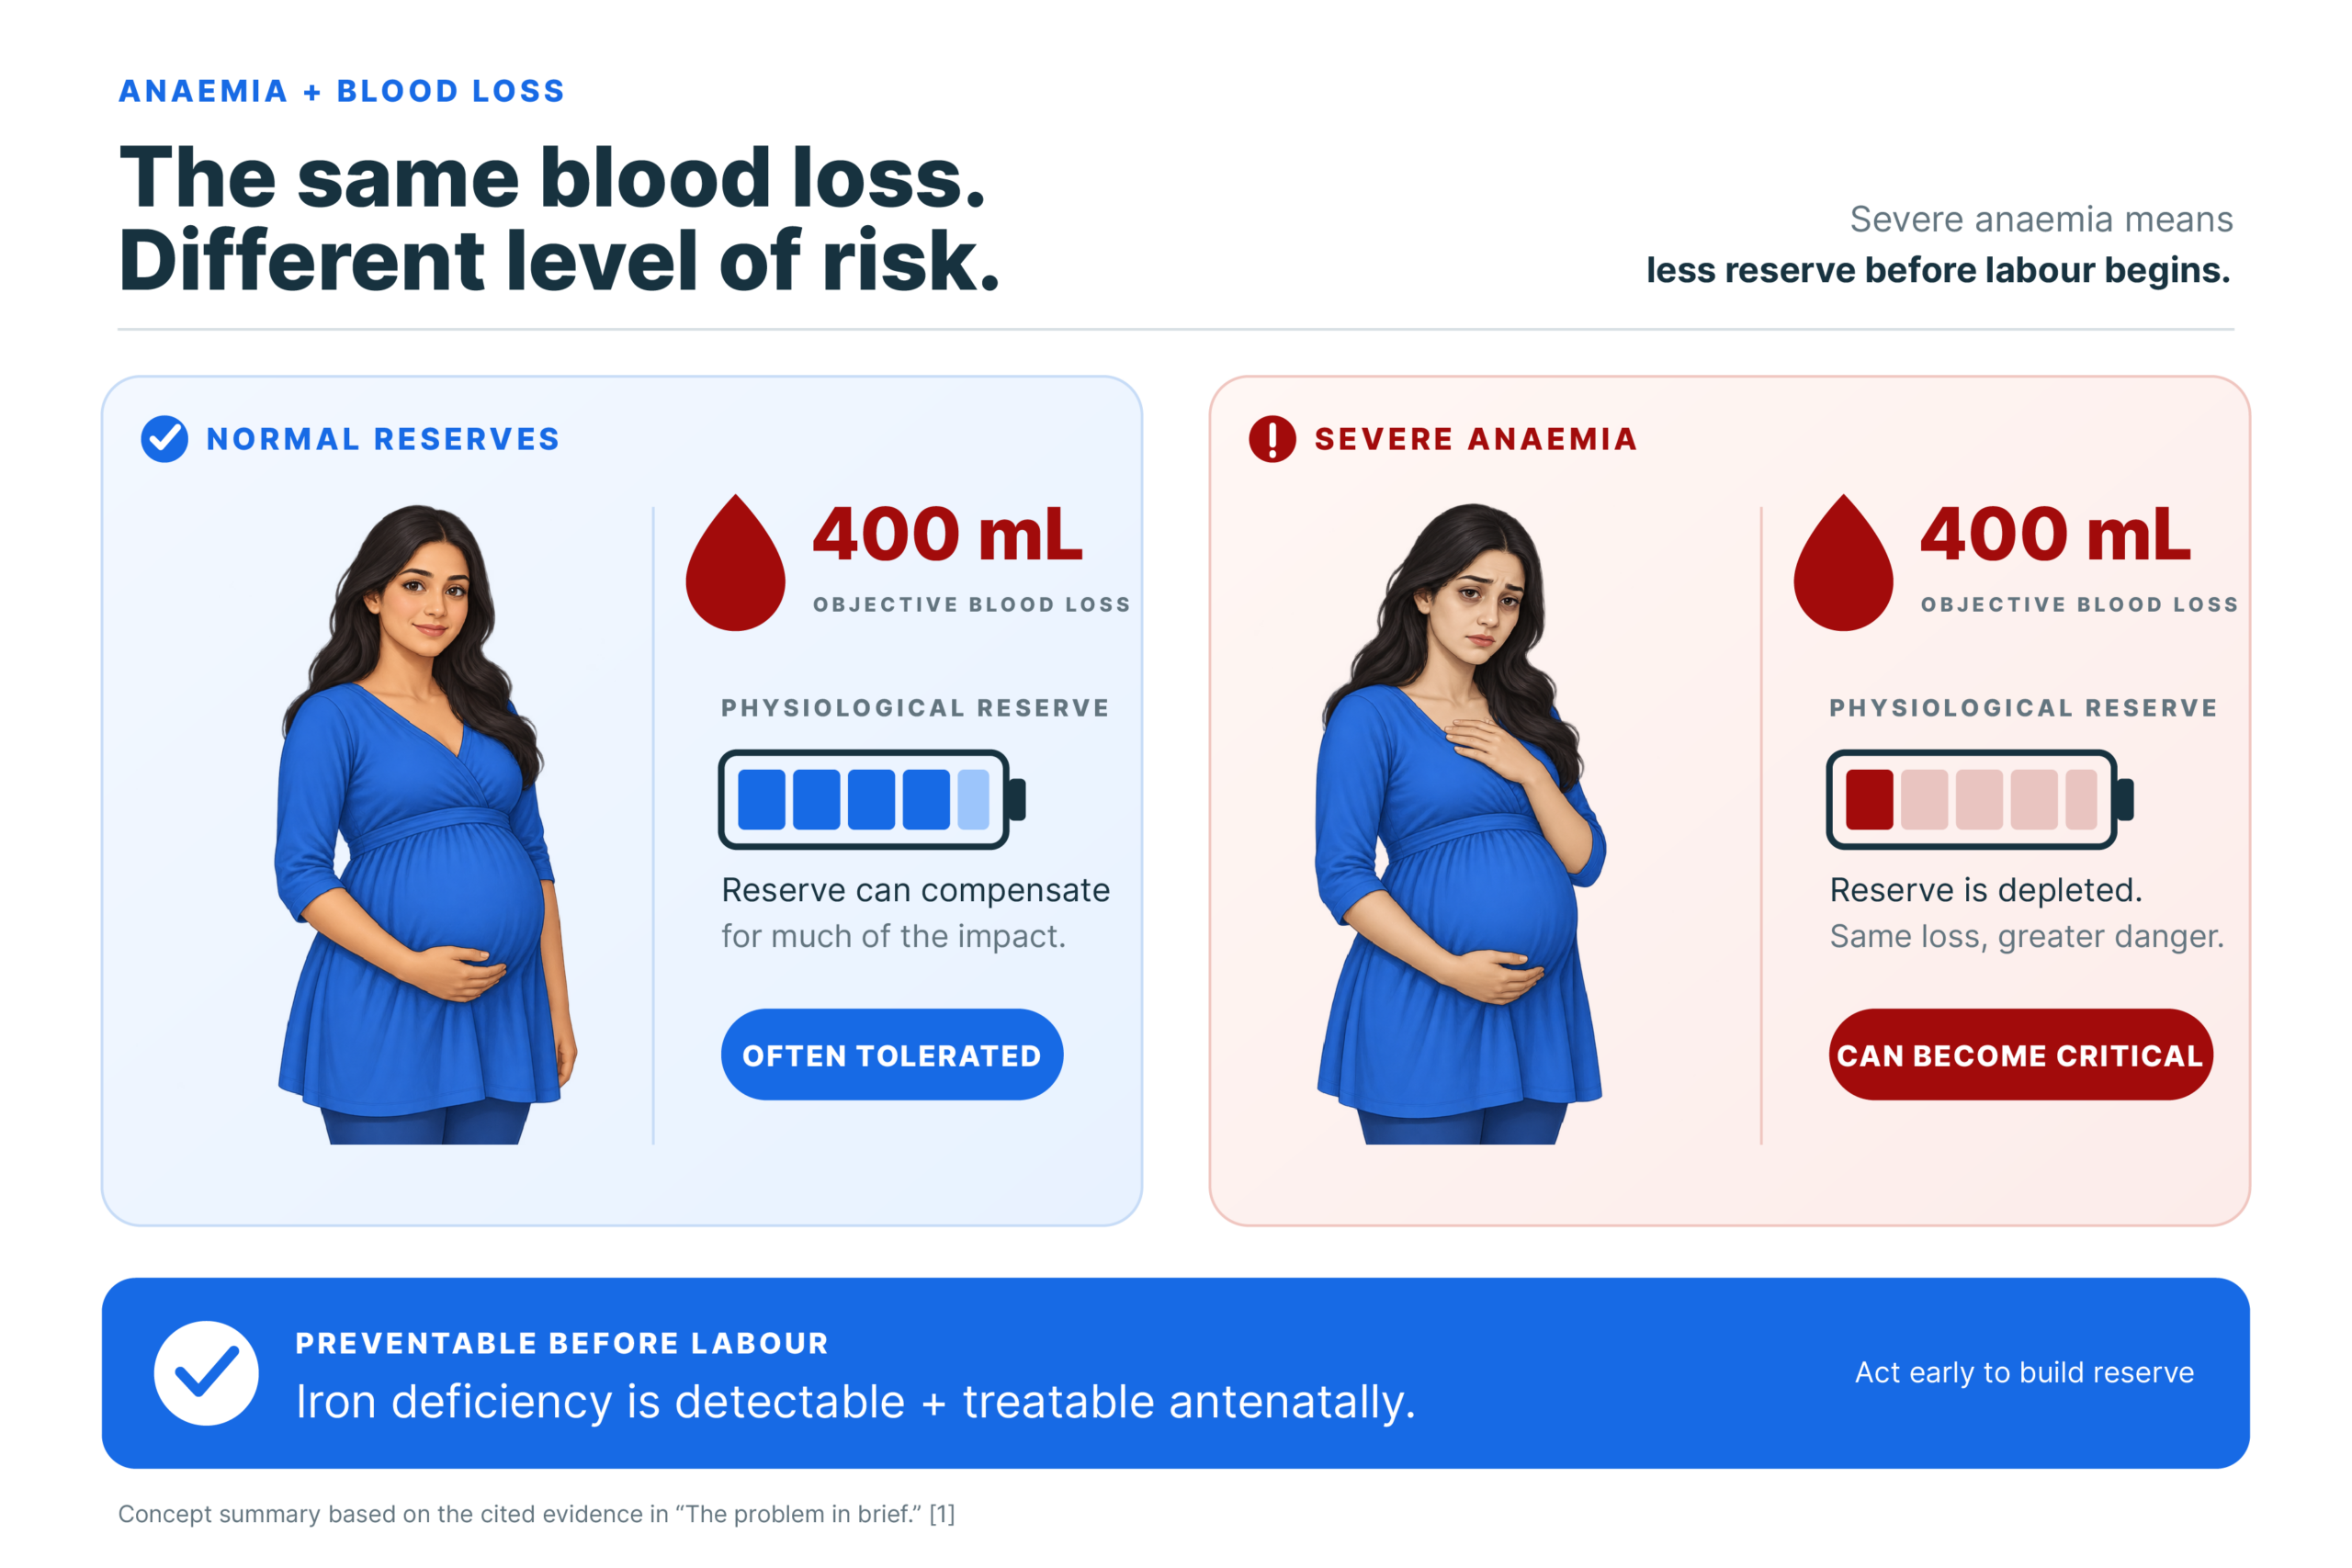
Anaemia influences a woman’s ability to withstand blood loss. This could be due to compensatory increases in cardiac output, placental size and vascularity; reductions in the oxygen carrying capacity of blood, compromising myometrial contractility; and impaired blood clotting [1]. In addition to this, a woman in labour with severe anaemia already starts with diminished reserves. As a result: the average 400 mL blood loss tolerated by a woman with normal reserves can become critical for a woman with severe anaemia.
Most pregnancy-related anaemia is due to iron deficiency, which is detectable and treatable well before labour, making the risks above preventable [1]. This page elaborates how anaemia can be prevented antenatally.
Offer contraception
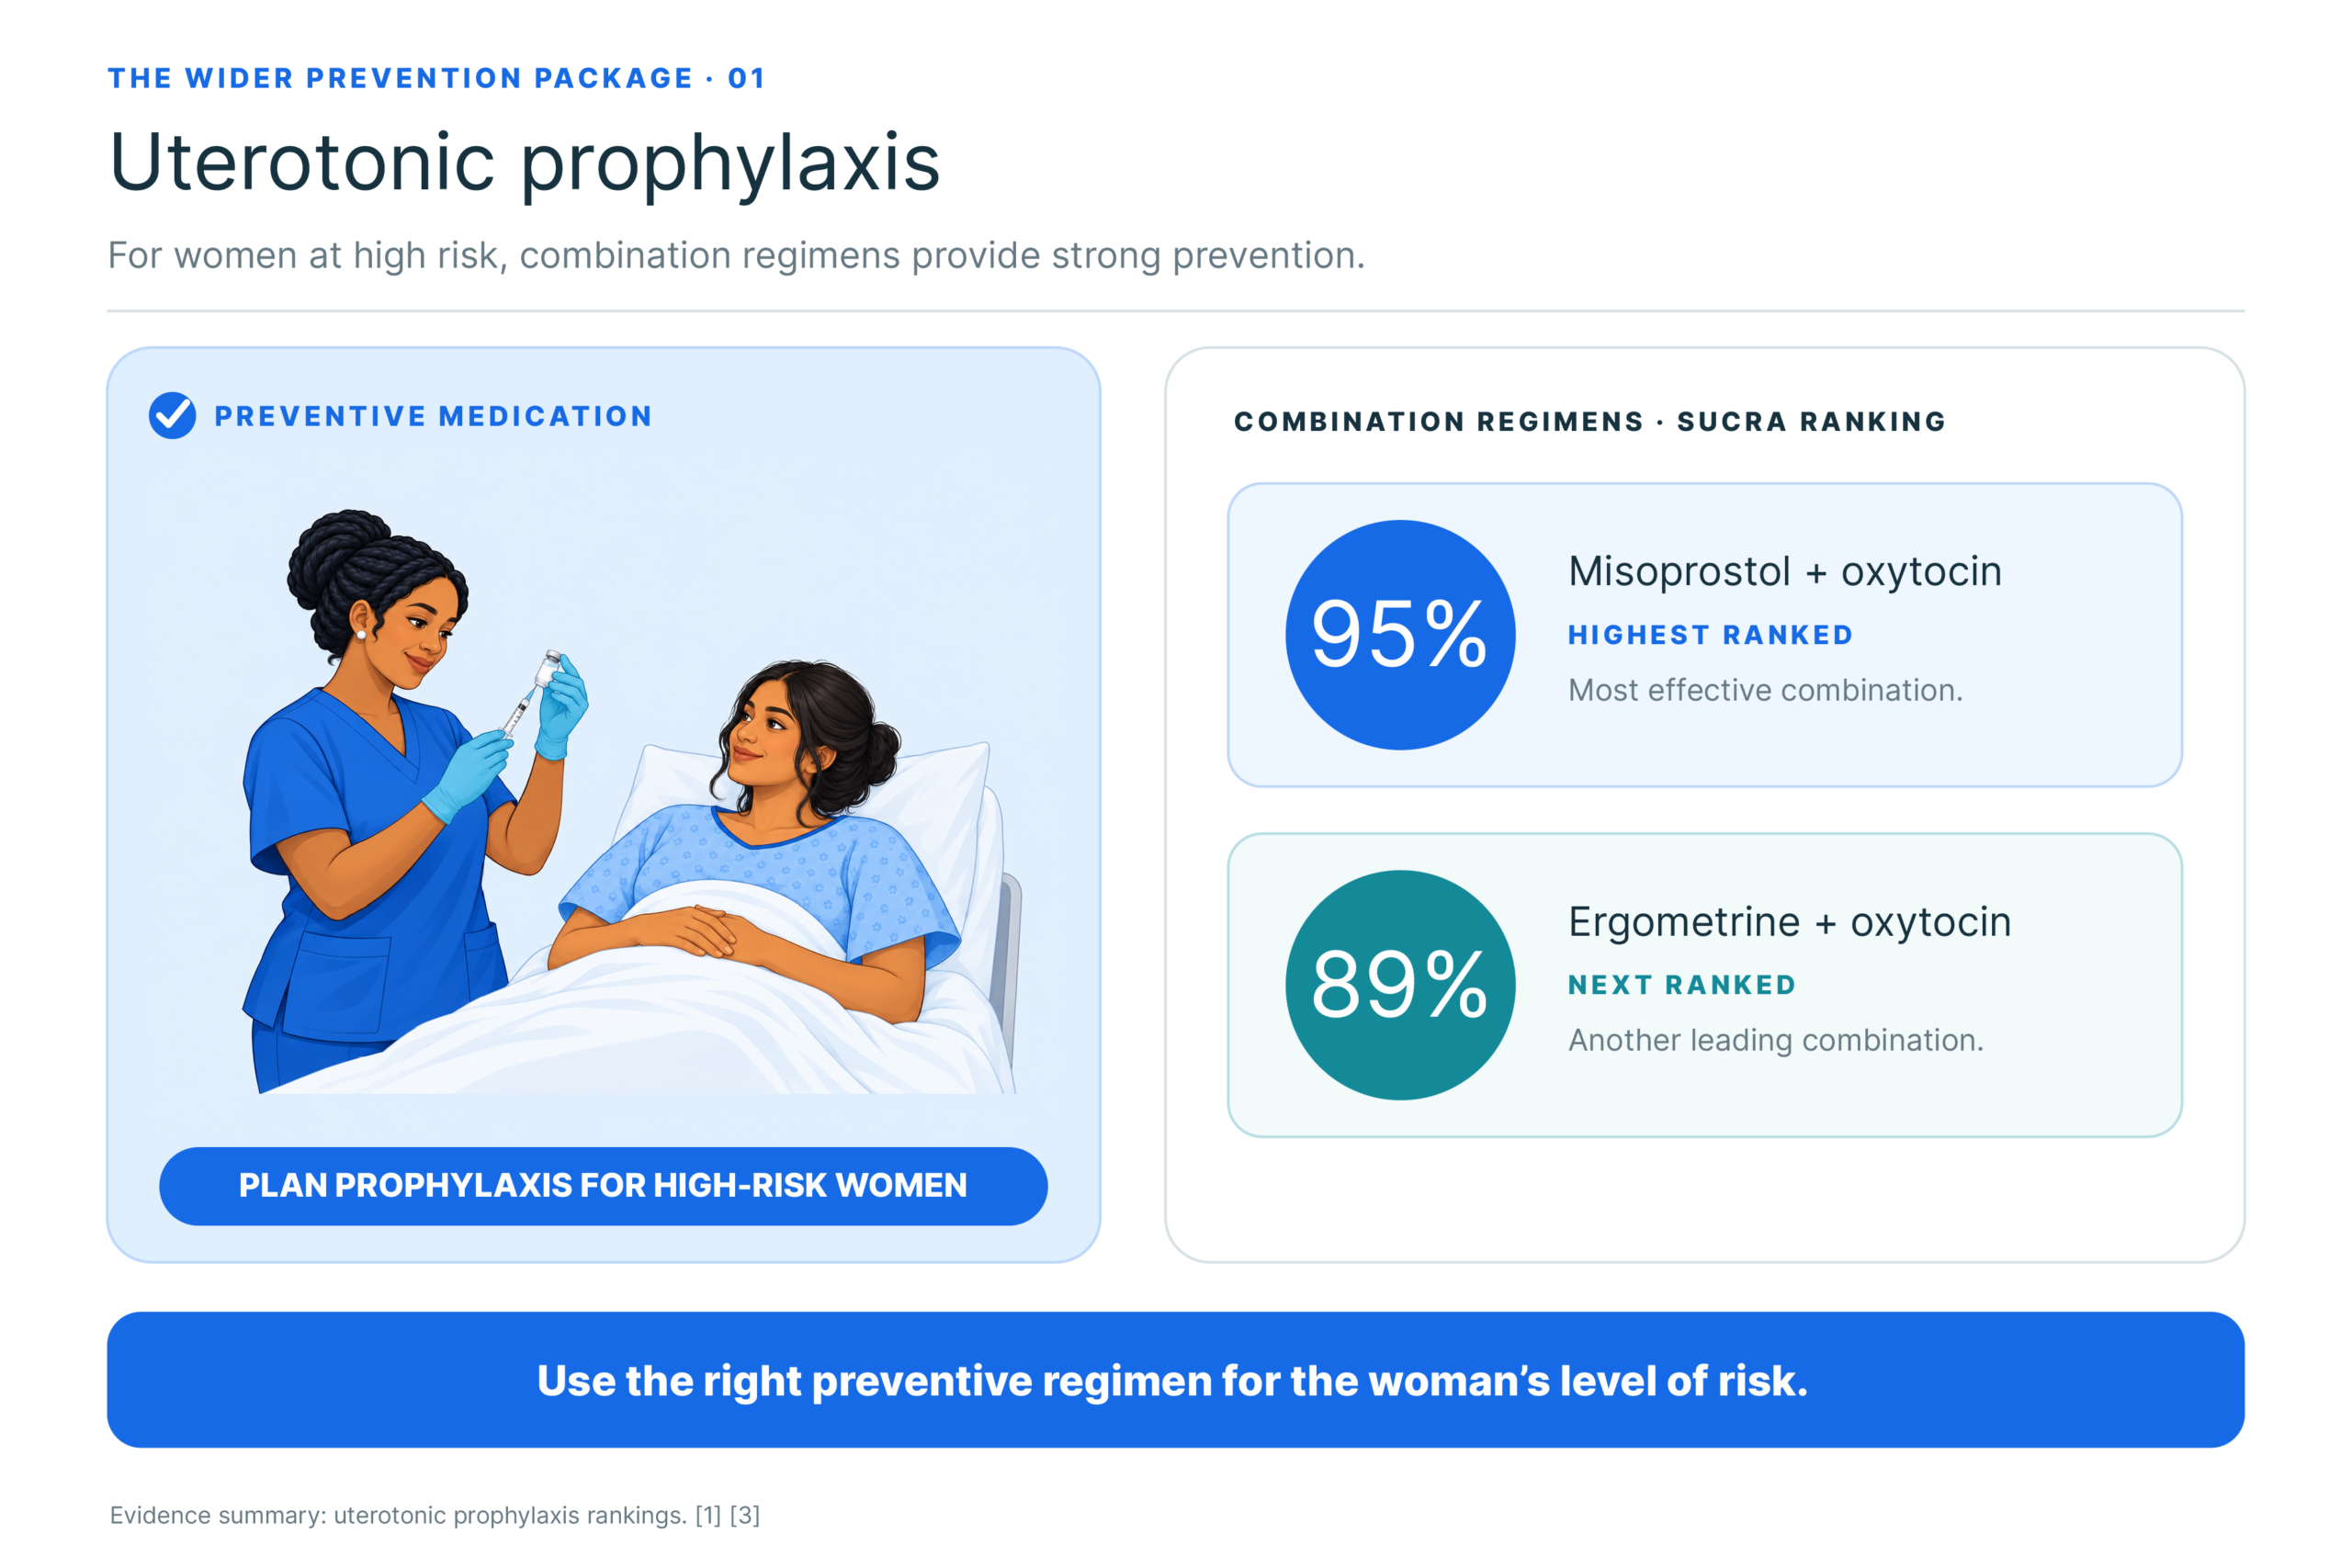
Provide uterotonic prophylaxis
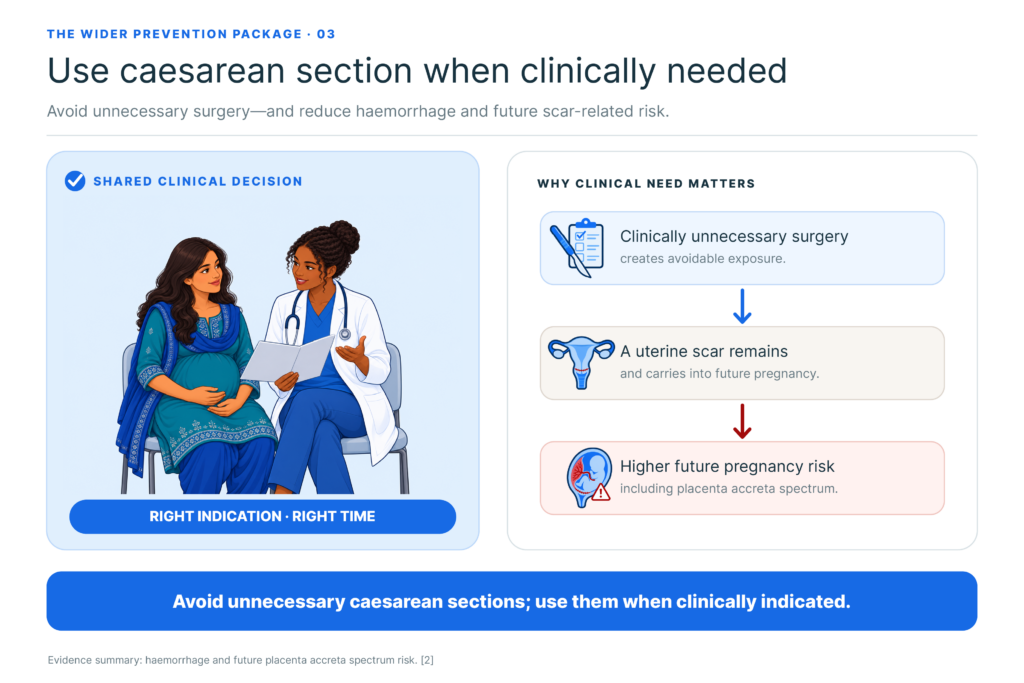
Avoid unnecessary caesarean sections
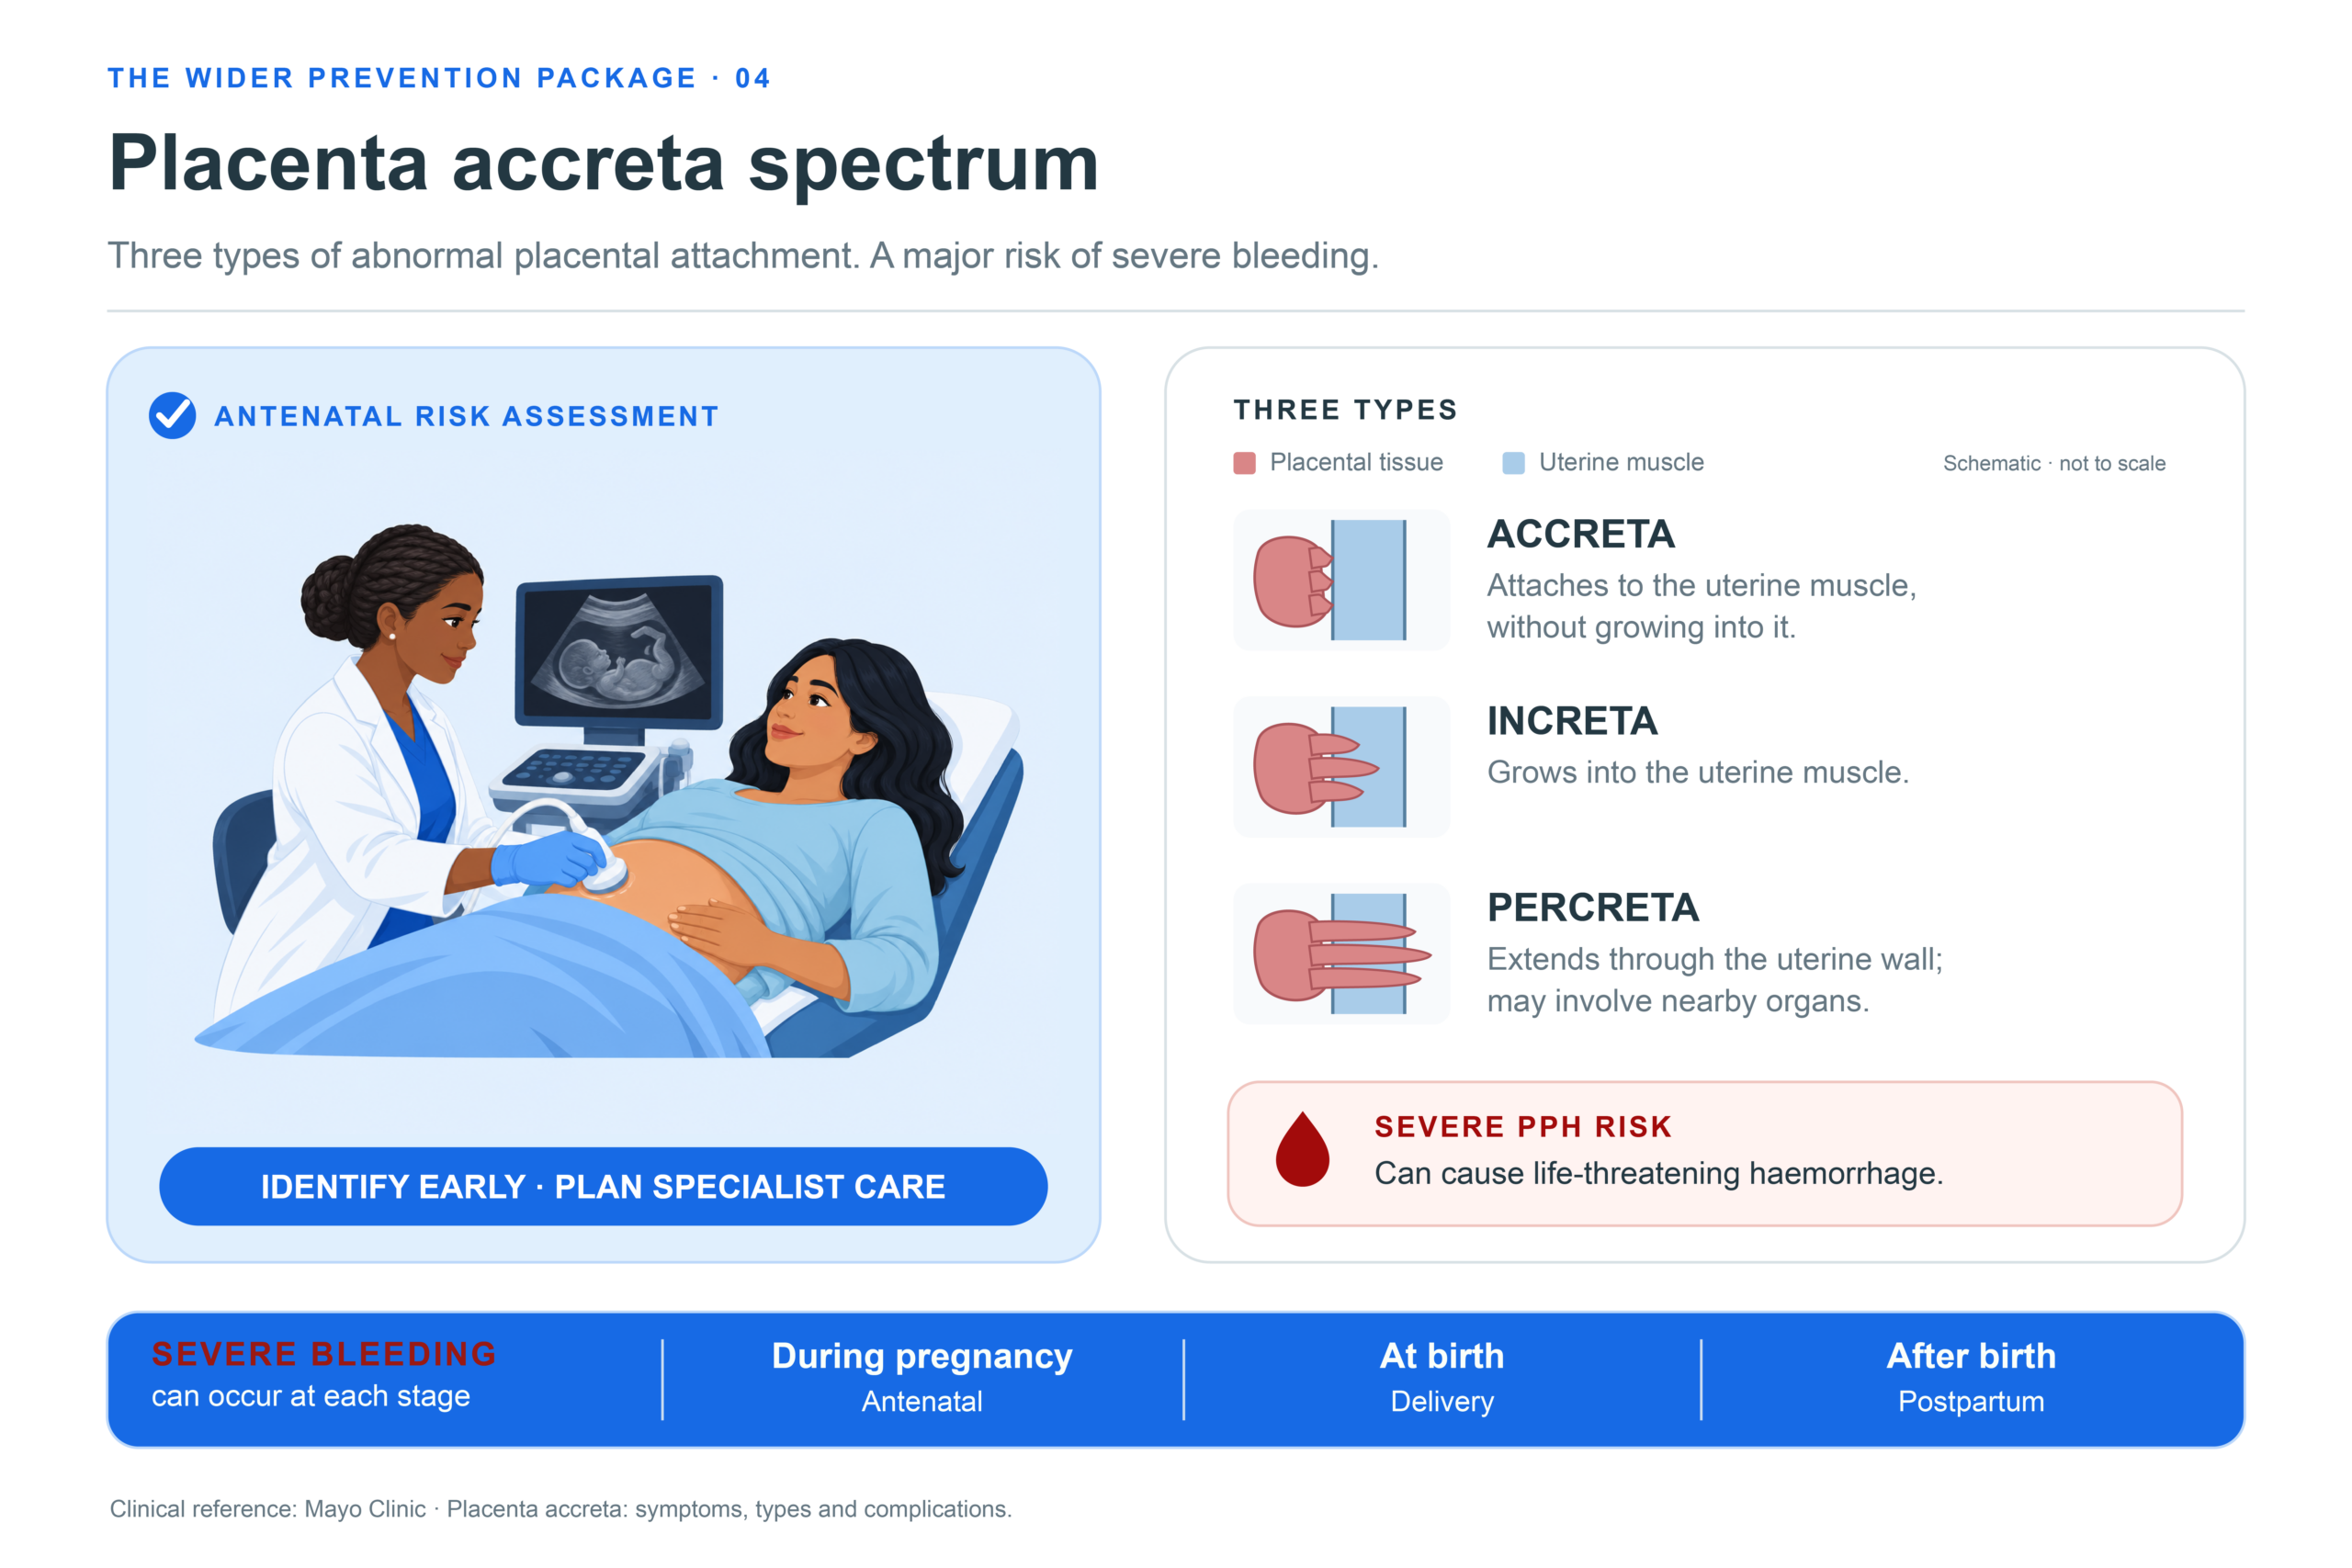
Prevent placenta accreta spectrum
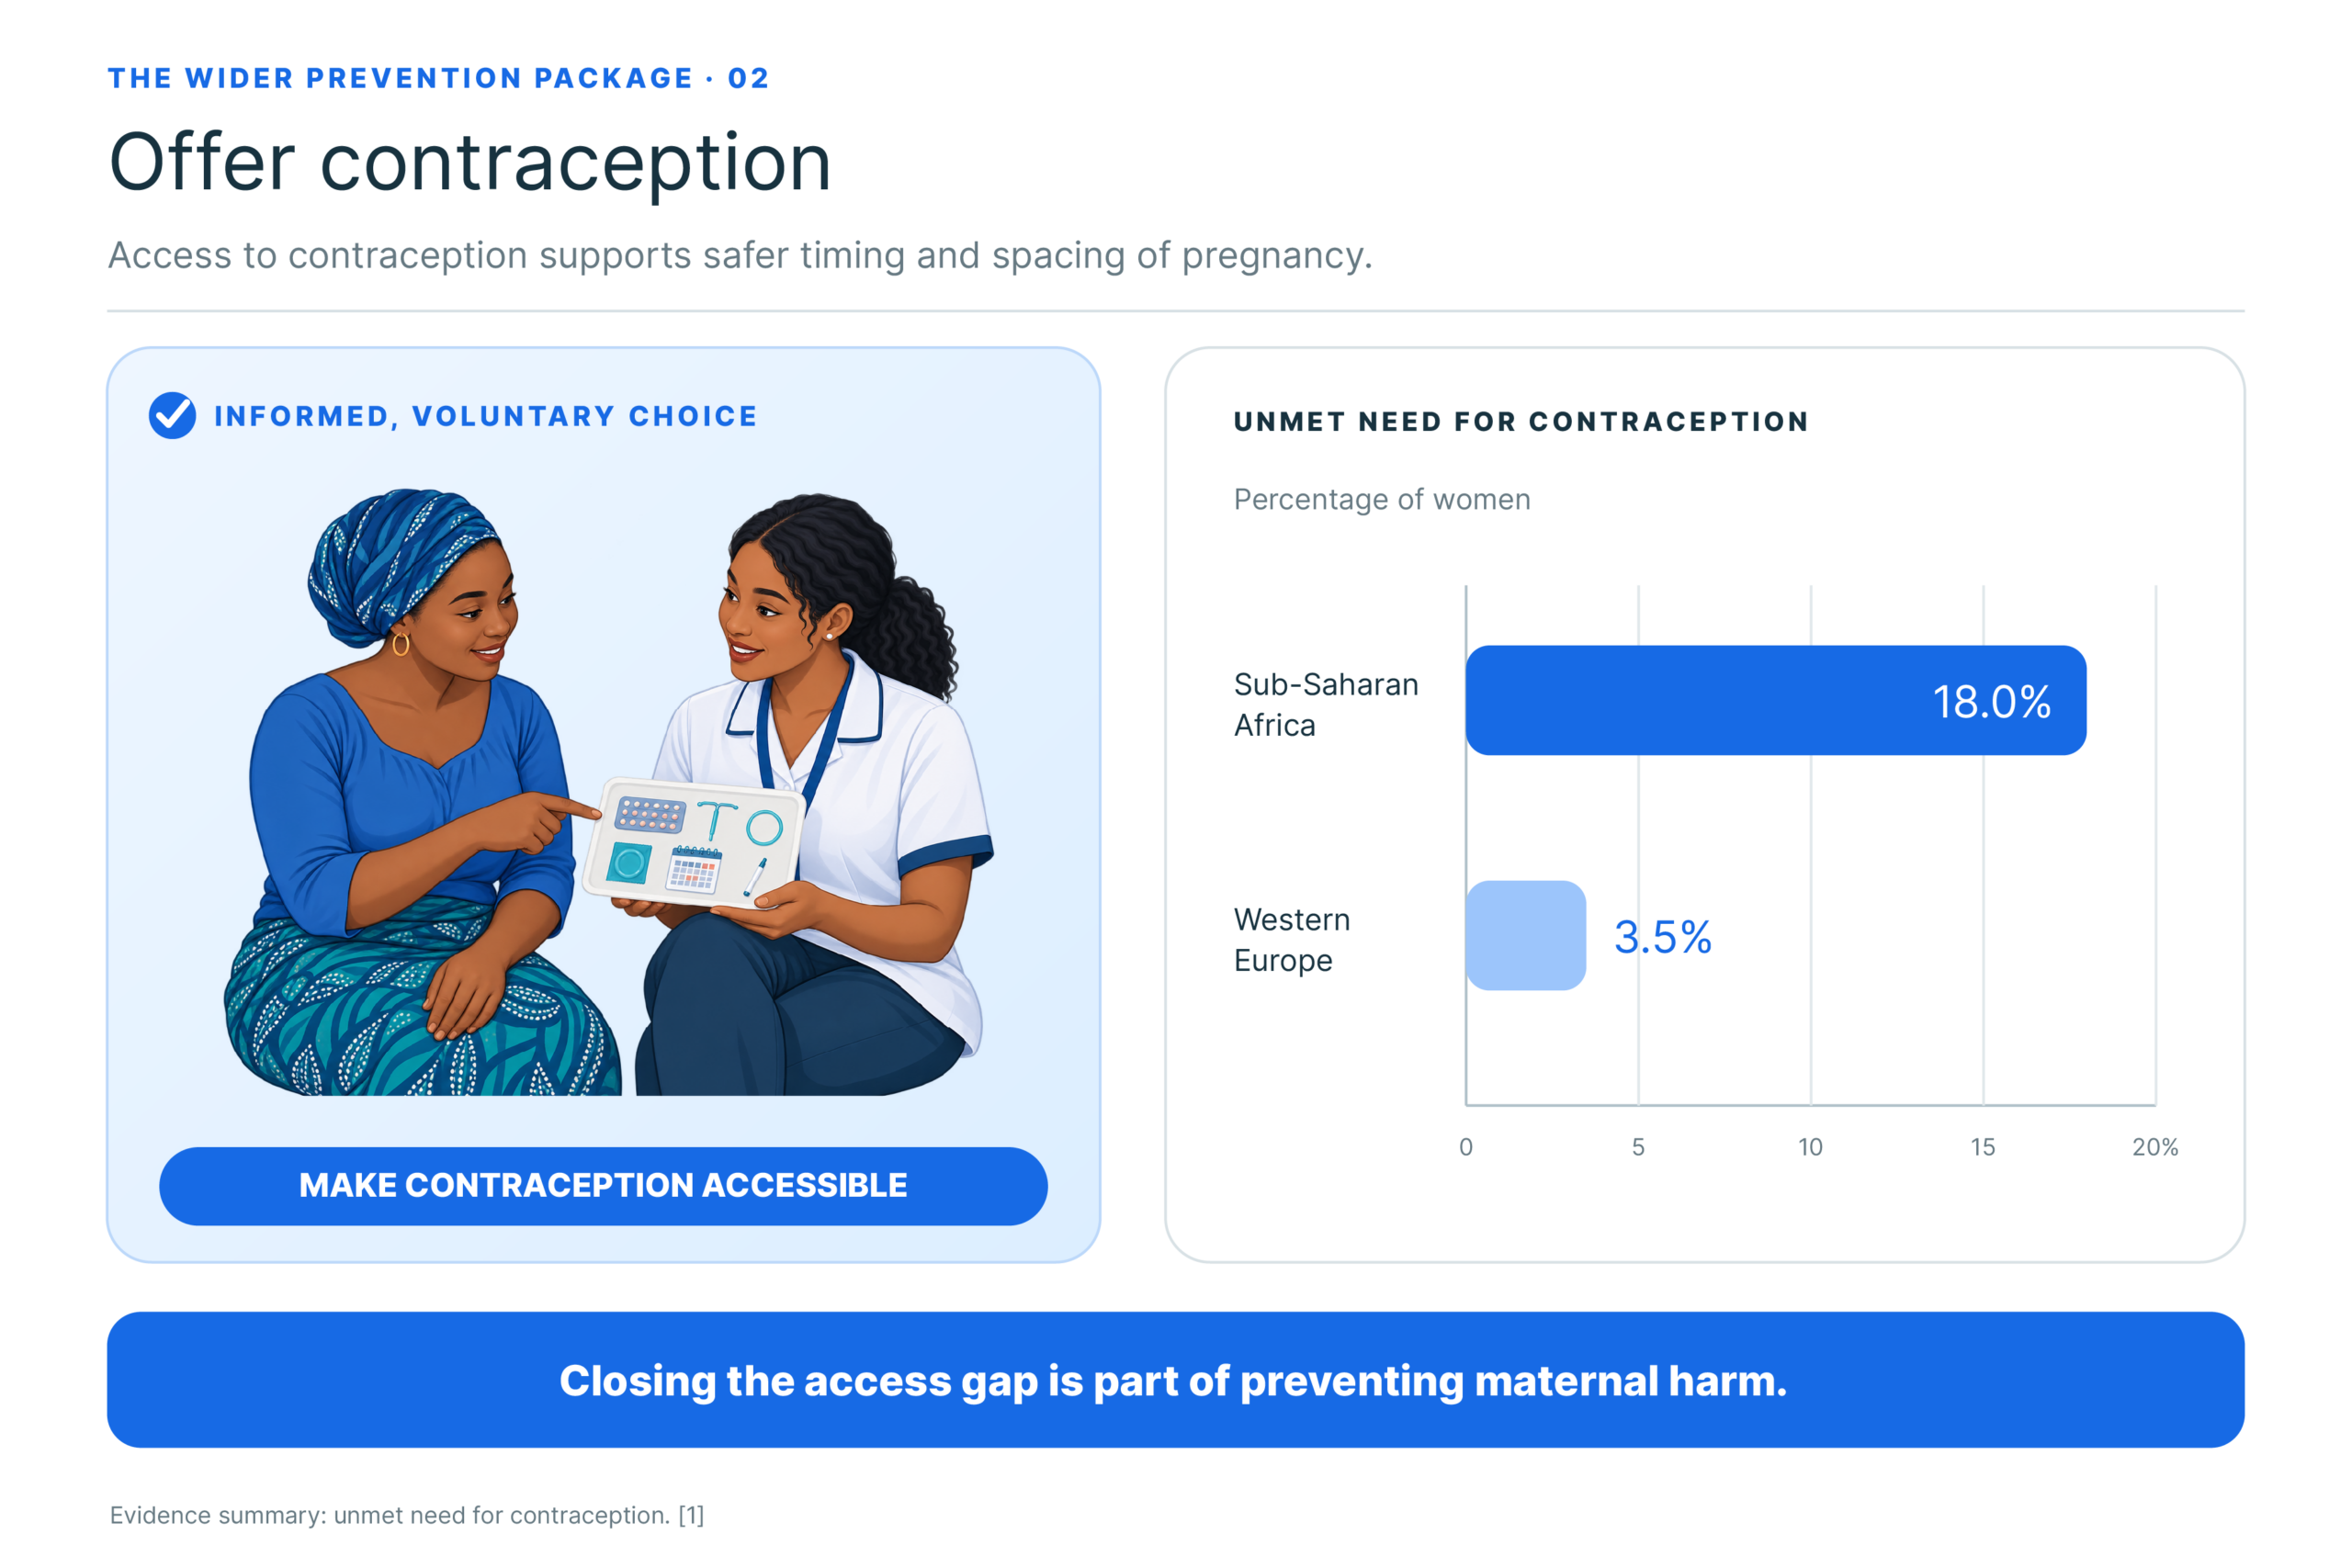
18.0% of women in sub-Saharan Africa face an unmet need for contraception, compared to only 3.5% in western Europe [1].
As well as increasing the risk of haemorrhage, caesarean sections increase the risk in future pregnancies of placenta accreta spectrum (abnormal placenta location) [2].
The Risk
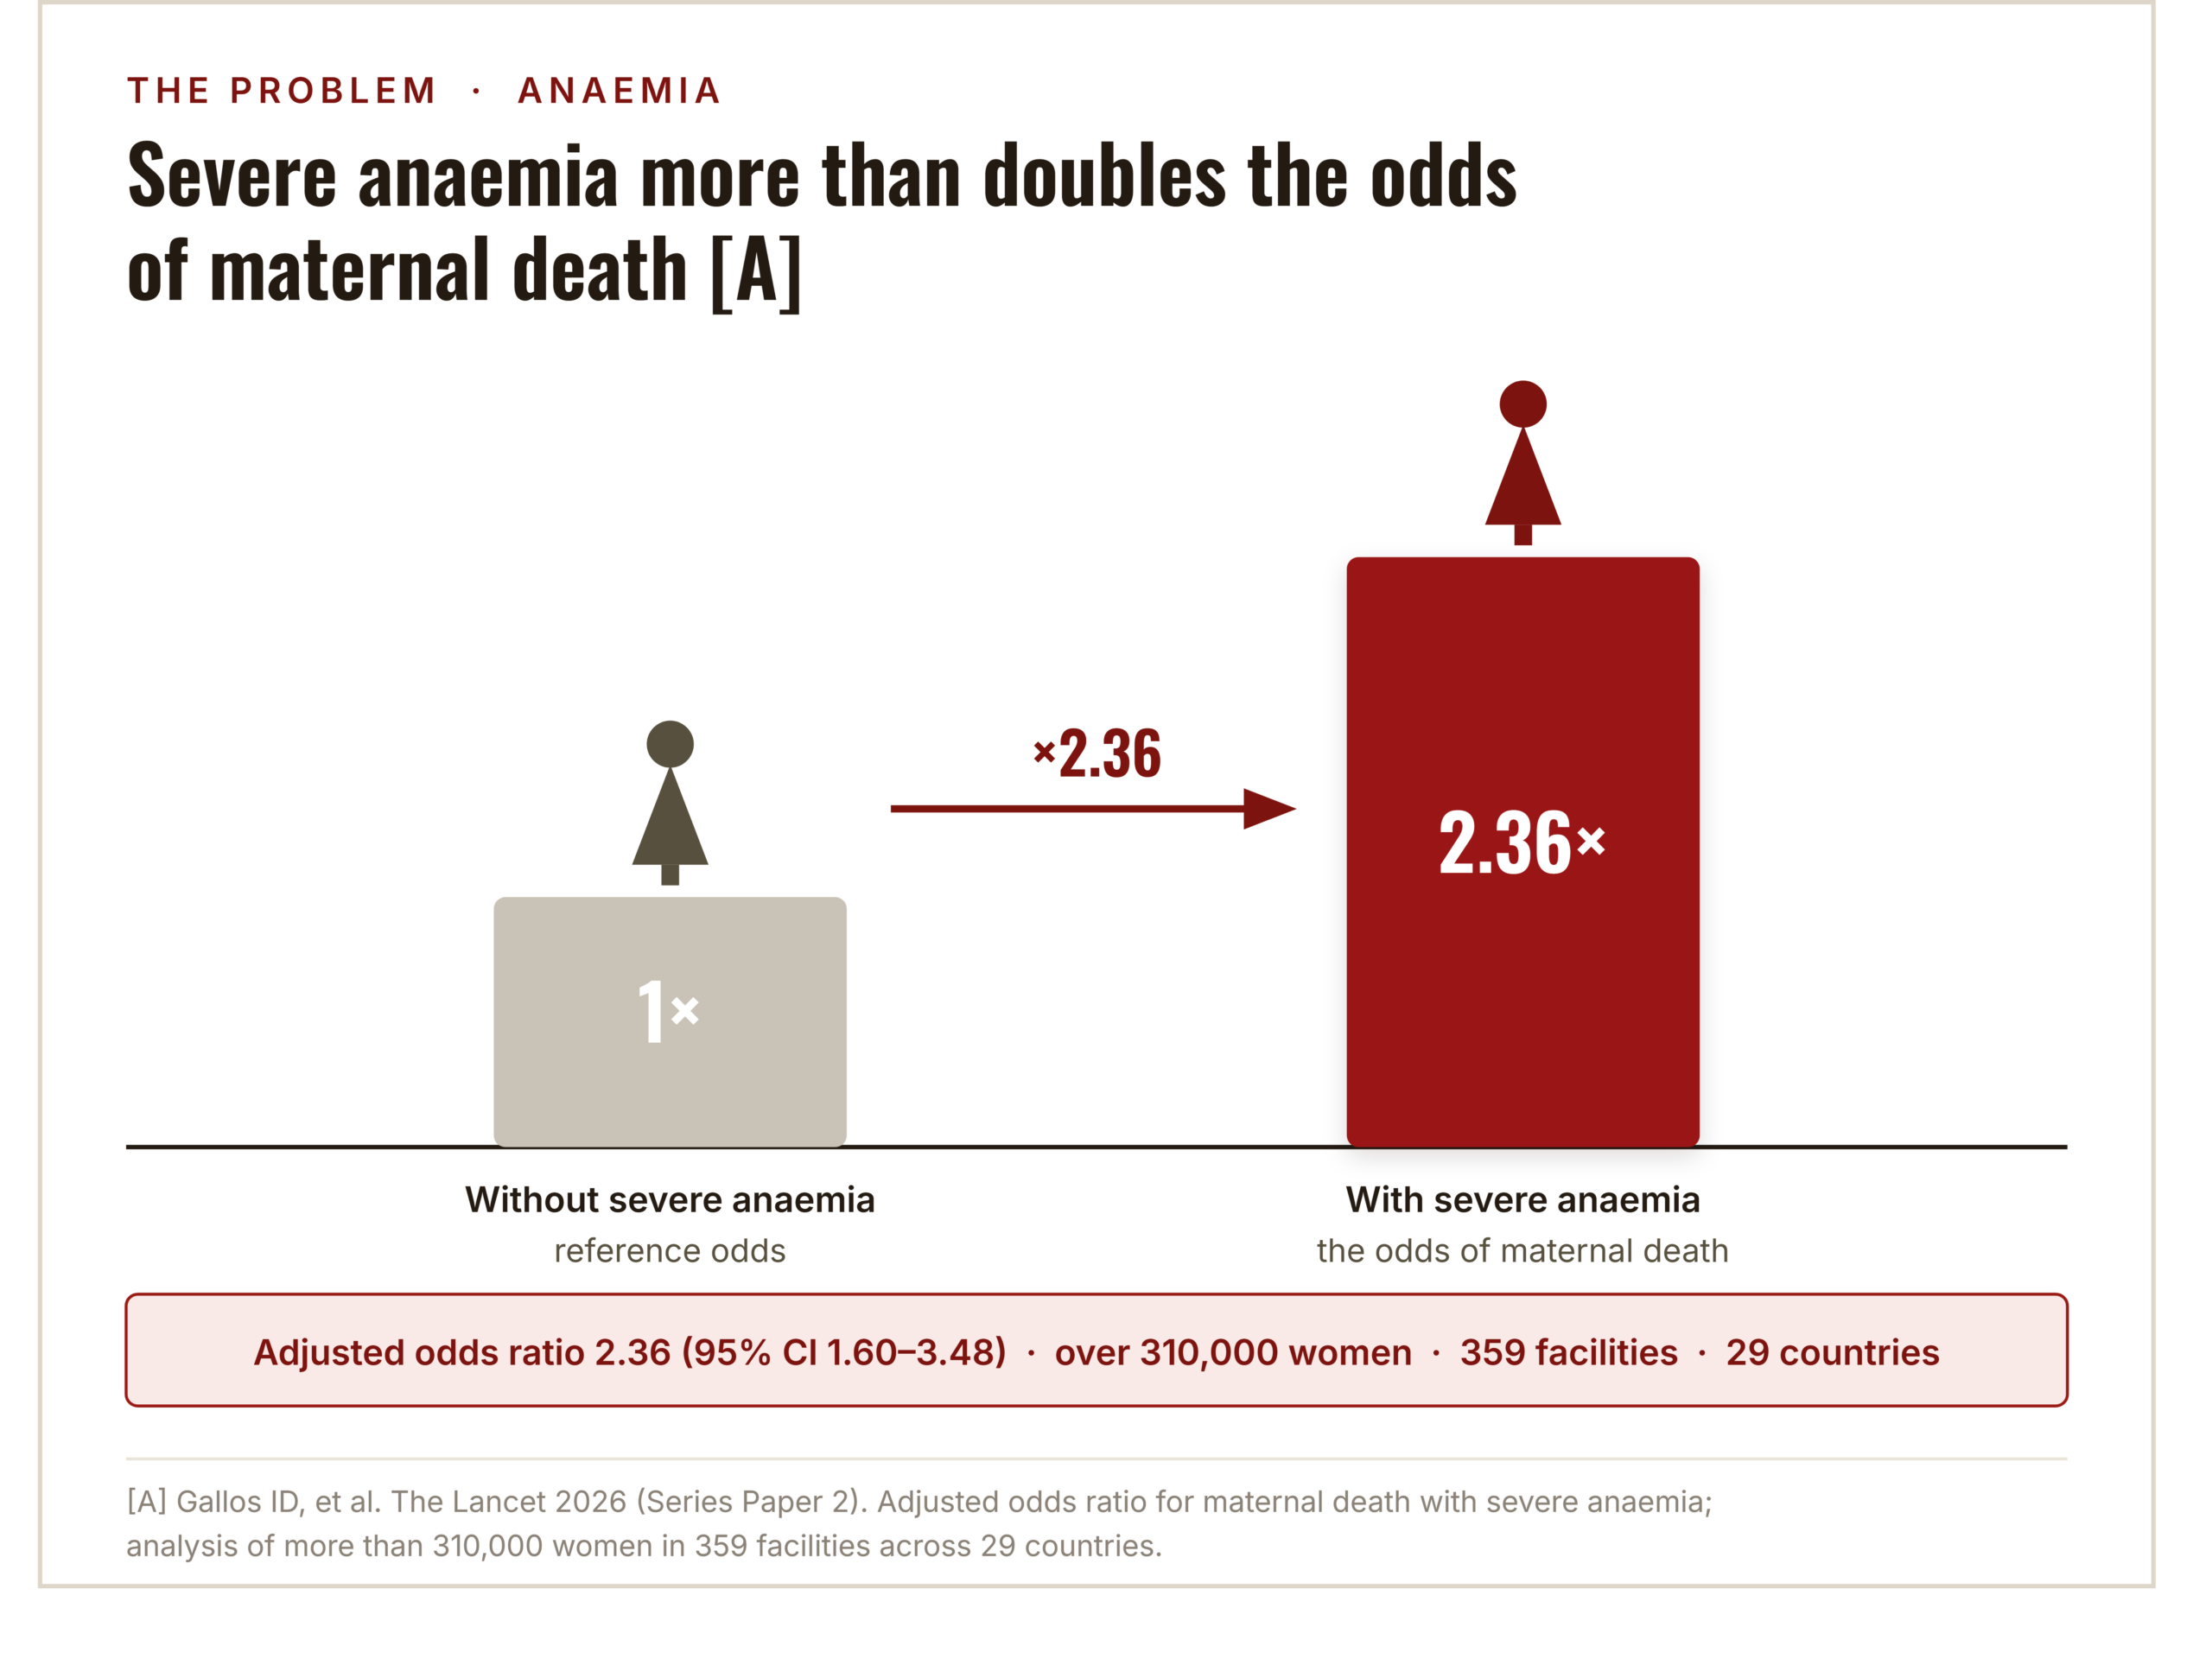
Anaemia increases the risks and effects of postpartum haemorrhage: women with anaemia face a 2.4-fold higher risk of death [1]. For survivors, the relationship does not end there; severe anaemia delays recovery and compounds the risk of future pregnancies [2]. Left unaddressed, the cycle continues throughout a woman’s reproductive life.
The Scale
The Solution
Among all risk factors for postpartum haemorrhage, anaemia holds a key place in guidelines as it can be easily identified and managed at low cost. Detection involves measuring haemoglobin, and treatments for anaemia can include:

The Policy
The consequences of leaving anaemia untreated reach beyond the woman herself, potentially reducing her capacity to work and care for her children [1].
Detecting and treating anaemia is therefore a strong choice for a ministry deciding where its maternal health budget should be directed.