
First response
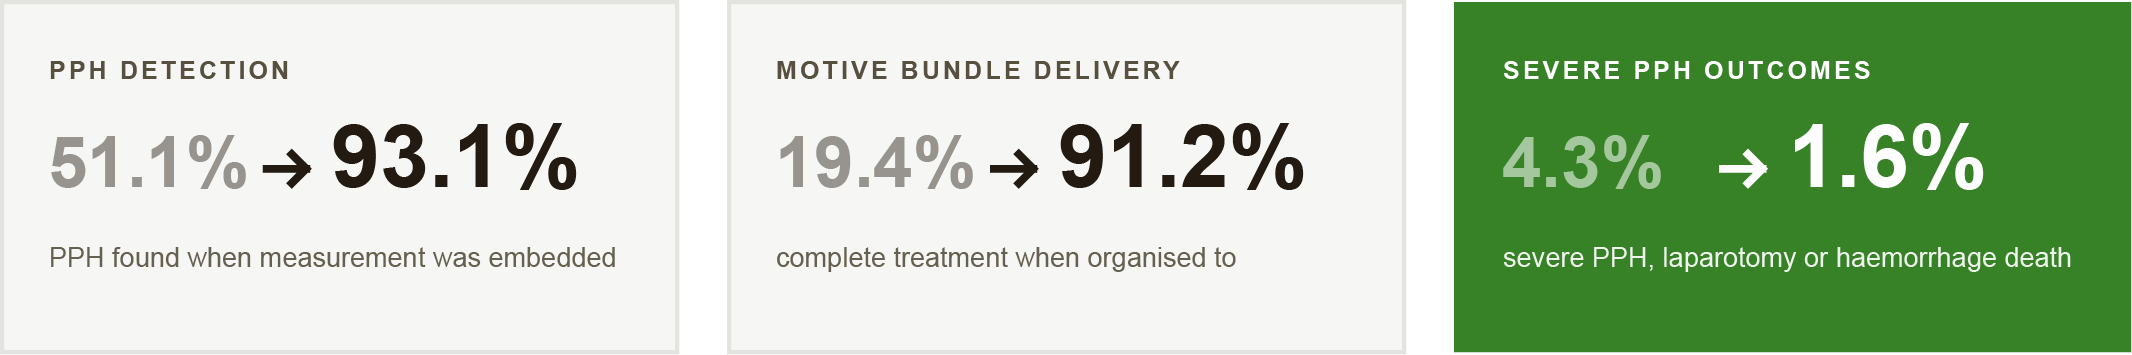
60% reduction in severe outcomes.
Refractory PPH
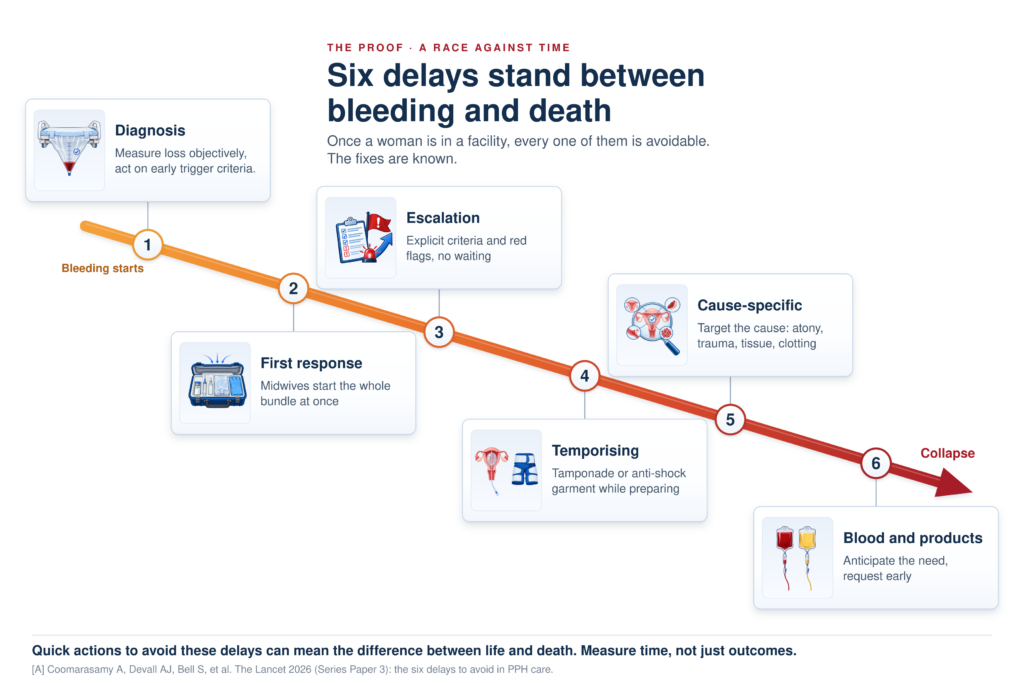
6 delays
The E-MOTIVE trial
All drugs and techniques listed here have long been part of established guidelines. E-MOTIVE focused on the importance of timing and combination: This was examined across 80 secondary hospitals in Kenya, Nigeria, South Africa, and Tanzania, involving 210,132 women having vaginal births. [1]
Why the E-MOTIVE bundle
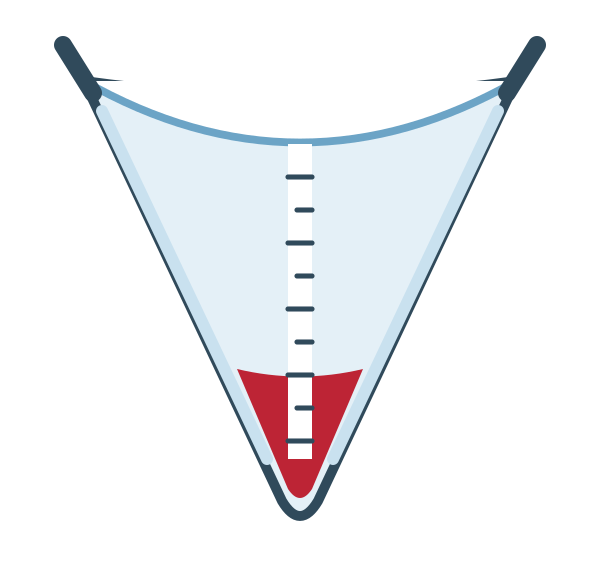
E-MOTIVE was designed and evaluated as an integrated intervention for the early detection and treatment of postpartum haemorrhage. The “E” component centres on early detection through routine use of a calibrated blood-collection drape, allowing blood loss to be measured objectively and predefined treatment thresholds to be recognised promptly.
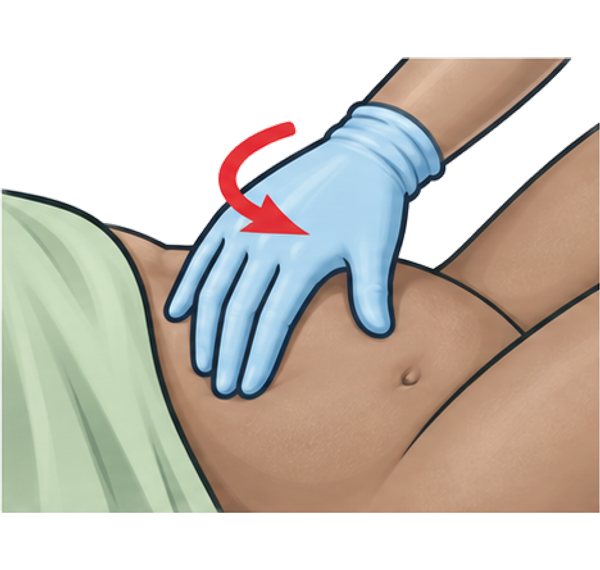
Once PPH is identified, the MOTIVE treatment bundle is initiated without delay: uterine Massage, Oxytocic drugs, Tranexamic acid, IntraVenous fluids, Vaginal/genital tract Examination, and escalation of care where required.
E-MOTIVE
E
Early detection of postpartum haemorrhage
▼
▼
Implementation strategies (ACTT)
Does E-MOTIVE apply effectively in real-world settings?
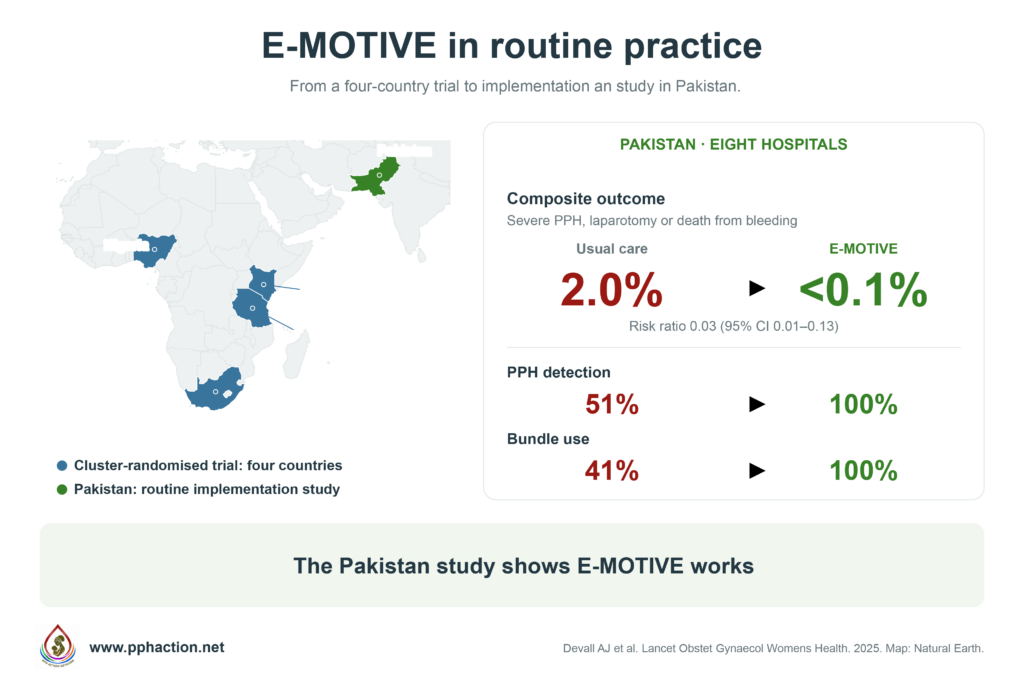
E-MOTIVE’s effectiveness has remained consistent outside trial settings. In Pakistan, a before-and-after study at eight hospitals assessed E-MOTIVE under routine conditions. The outcome of severe PPH, laparotomy for bleeding, or death from bleeding fell from 20 cases per 1,000 births with usual care to fewer than 1 per 1,000 with the E-MOTIVE intervention, a 97% reduction in risk. PPH detection improved from half of all cases to every case, and first-response bundle use from 4 in 10 women to all women. [4].
The overall evidence includes one large trial across four African countries, an implementation study in Pakistan.
The cost of E-MOTIVE
An economic evaluation conducted alongside the trial showed that the E-MOTIVE intervention was cost-effective [3]. The adjusted cost difference was US$0.30 per patient (95% CI −2.31 to 2.78), with an estimated US$11.83 per case of severe PPH prevented, and US$113.91 per disability-adjusted life-year (DALY) averted.
When the willingness-to-pay threshold surpasses roughly US$1,500 per DALY averted, the probability of cost-effectiveness exceeds 80% [3]. Since costs and thresholds vary between countries, ministries should combine this evidence with local budget-impact analysis.
The economic analysis dispels the assumption that better outcomes necessarily entail higher costs beyond what the system can afford.

The status of national postpartum haemorrhage guidelines, country by country.
Activities at local and national level to train, implement and scale up E-MOTIVE.
Initiatives and efforts taken up by national or local government and ministerial bodies to implement E-MOTIVE.
E-MOTIVE training activity across implementing countries.
Manufacturers producing the calibrated blood-collection drapes used in E-MOTIVE.
In practice · Same woman. Same blood loss. Different outcomes.
USUAL CARE
THE E-MOTIVE PATHWAY

Estimated blood loss
Blood loss is estimated visually and recorded as normal.

Objective blood loss measurement
The drape reads 520 mL at thirty minutes. Based on this measurement:

Delayed diagnosis
An hour on, the woman is pale and tachycardic; the blood loss is re-estimated at “maybe 600”.

PPH is diagnosed
The first-response bundle is initiated within fifteen minutes of diagnosis [6].
Response begins
A uterotonic is given.
MOTIVE bundle
Uterine massage begins, oxytocics, tranexamic acid, IV fluids are administered,

After review
Tranexamic acid is considered at the next review.

Examination and escalation
and the examination reveals a small vaginal tear, which is repaired in the room [5].
By the time the diagnosis is confirmed, the woman is experiencing severe PPH, and the response is escalation to theatre.

Bleeding is stopped or escalation begins.

When the first response treatment fails
Examination and Escalation
Refractory postpartum haemorrhage refers to bleeding that does not respond to the first response treatment. Life-threatening postpartum haemorrhage can lead to shock, collapse or organ failure [2]. Recognisable warning signs include drowsiness, confusion, breathlessness, low urine output, blood loss of 1,500 mL or more, pulse above 110, systolic pressure below 90 mmHg, and a shock index of 1.7 or higher [2].
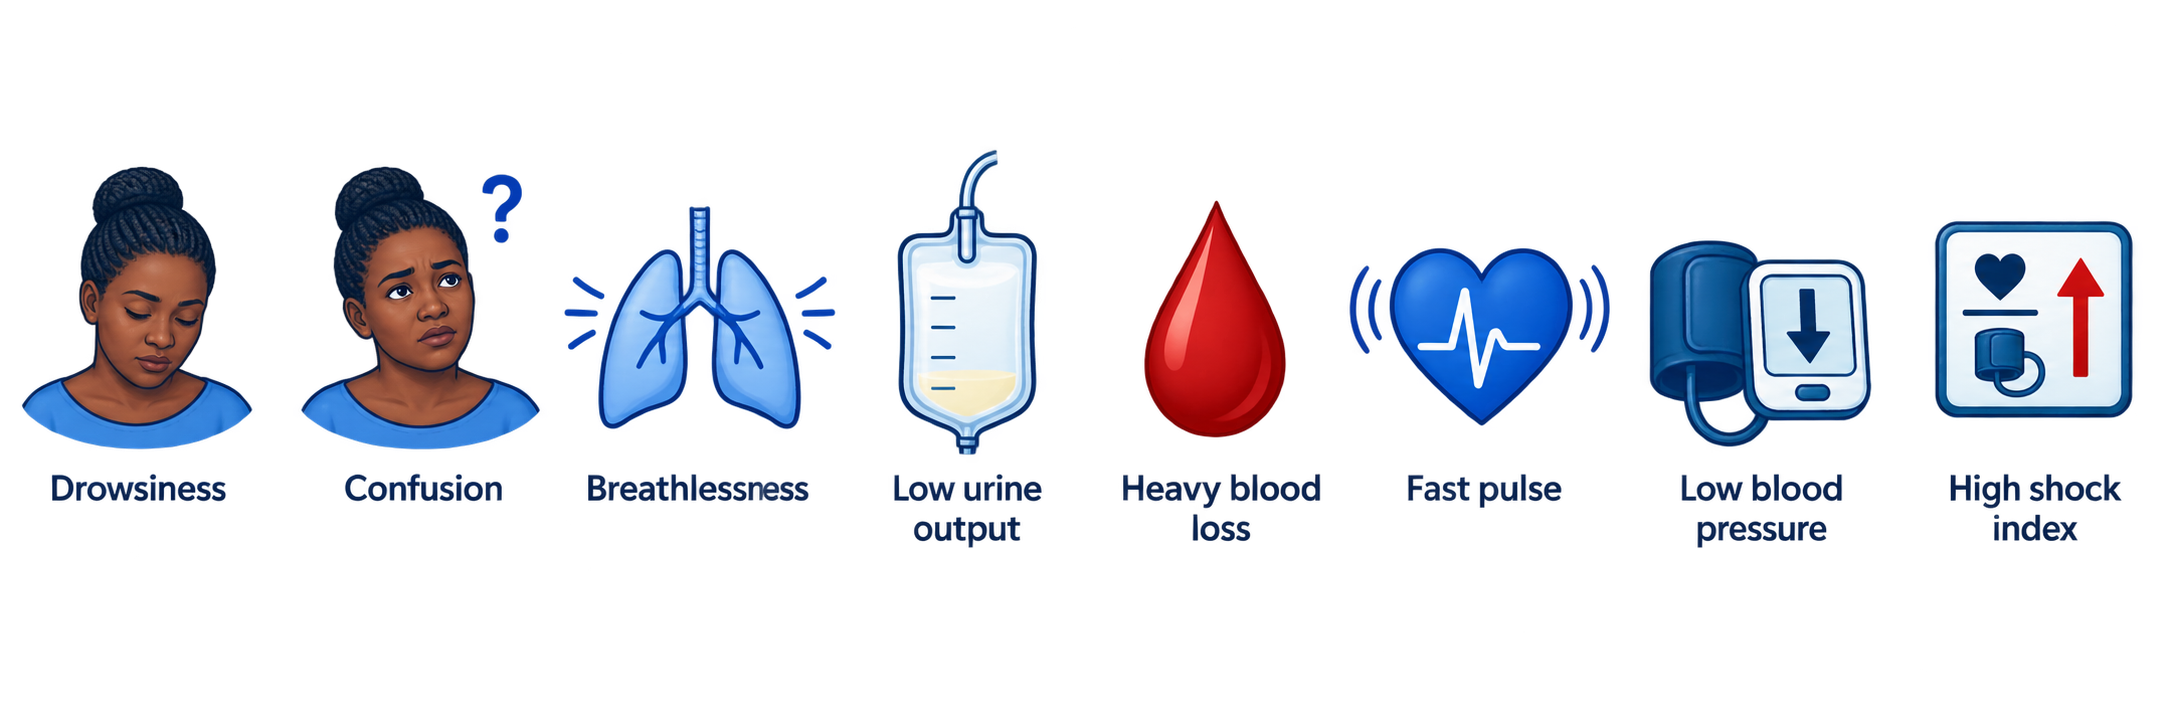
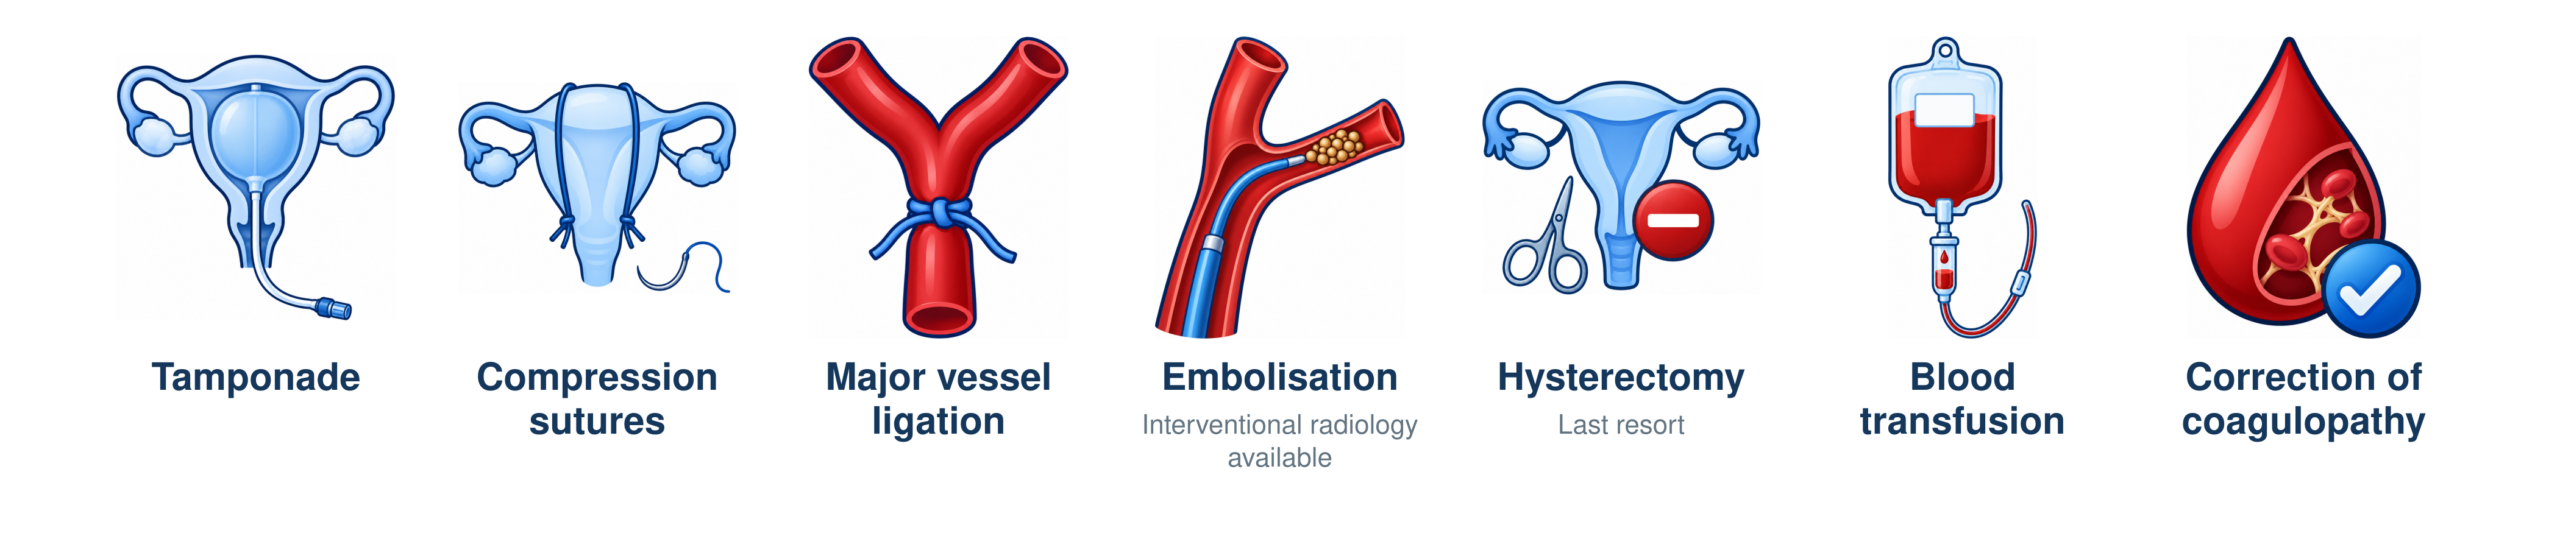
Once one or more of these signs appear, surgical and haematological interventions are necessary: tamponade, compression sutures, major vessel ligation, embolisation (where an interventional radiologist is available), and hysterectomy as a last resort. These interventions should be supported by transfusions and correction of coagulopathy, which can develop early and rapidly [2] [7].
Where healthcare systems can fail
A facility might diagnose postpartum haemorrhage accurately, but delays in treating it (for example, low-quality oxytocin) can still lead to a woman’s death. Additional factors include the unavailability of blood transfusion services or slow referral processes.
South Africa’s triennial confidential enquiries into maternal deaths [9] revealed that 70% of obstetric haemorrhage deaths involved avoidable healthcare factors, such as insufficient blood supply, transport delays between facilities, and overburdened services causing management delays [2].
TO REVIEW
Measuring intervals such as the time from birth to PPH to diagnosis, from diagnosis to first response treatment, and from request for blood to transfusion pinpoints where delays occur within the treatment pathway [8]. Each delay has a specific solution.
In practice · Two versions of the same hour
In practice · An illustrative scenario
An illustrative scenario based on maternal death review findings.
Escalation · An illustrative scenario
Same blood loss. A different response.
500 mL estimated. 860 mL actual. Treatment starts; bleeding continues.
WHERE THE SYSTEM LOSES HER
WHERE THE SYSTEM CATCHES HER

No agreed red flags
No automatic escalation; senior opinion is 40 minutes away.

Automatic escalation
Red flags displayed; the call is automatic at 1,000 mL with a rising shock index.

Bleeding continues
Blood loss increases while the team waits for senior review.
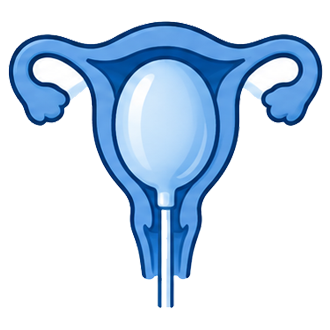
Tamponade buys time
A temporary measure while definitive care is arranged.

Blood ordered late
Blood is requested only once she is already in shock.

Blood already prepared
Cross-matched in advance under the facility’s agreed protocol.

Two hours to referral
Transport to the referral hospital takes two hours.

Ready for theatre care
She reaches theatre warm, oxygenated and correctable.
Make escalation a system response.
Illustrative scenario. The 1,000 mL escalation point shown is a local rule in this example.

