
05 · Start Before Birth · Prevention and anaemia
The risk is set
before labour begins.
The previous four pages explained how to respond when a woman haemorrhages. This page focuses on prevention: actions a health system can take prior to a woman entering a labour room.
The problem in brief
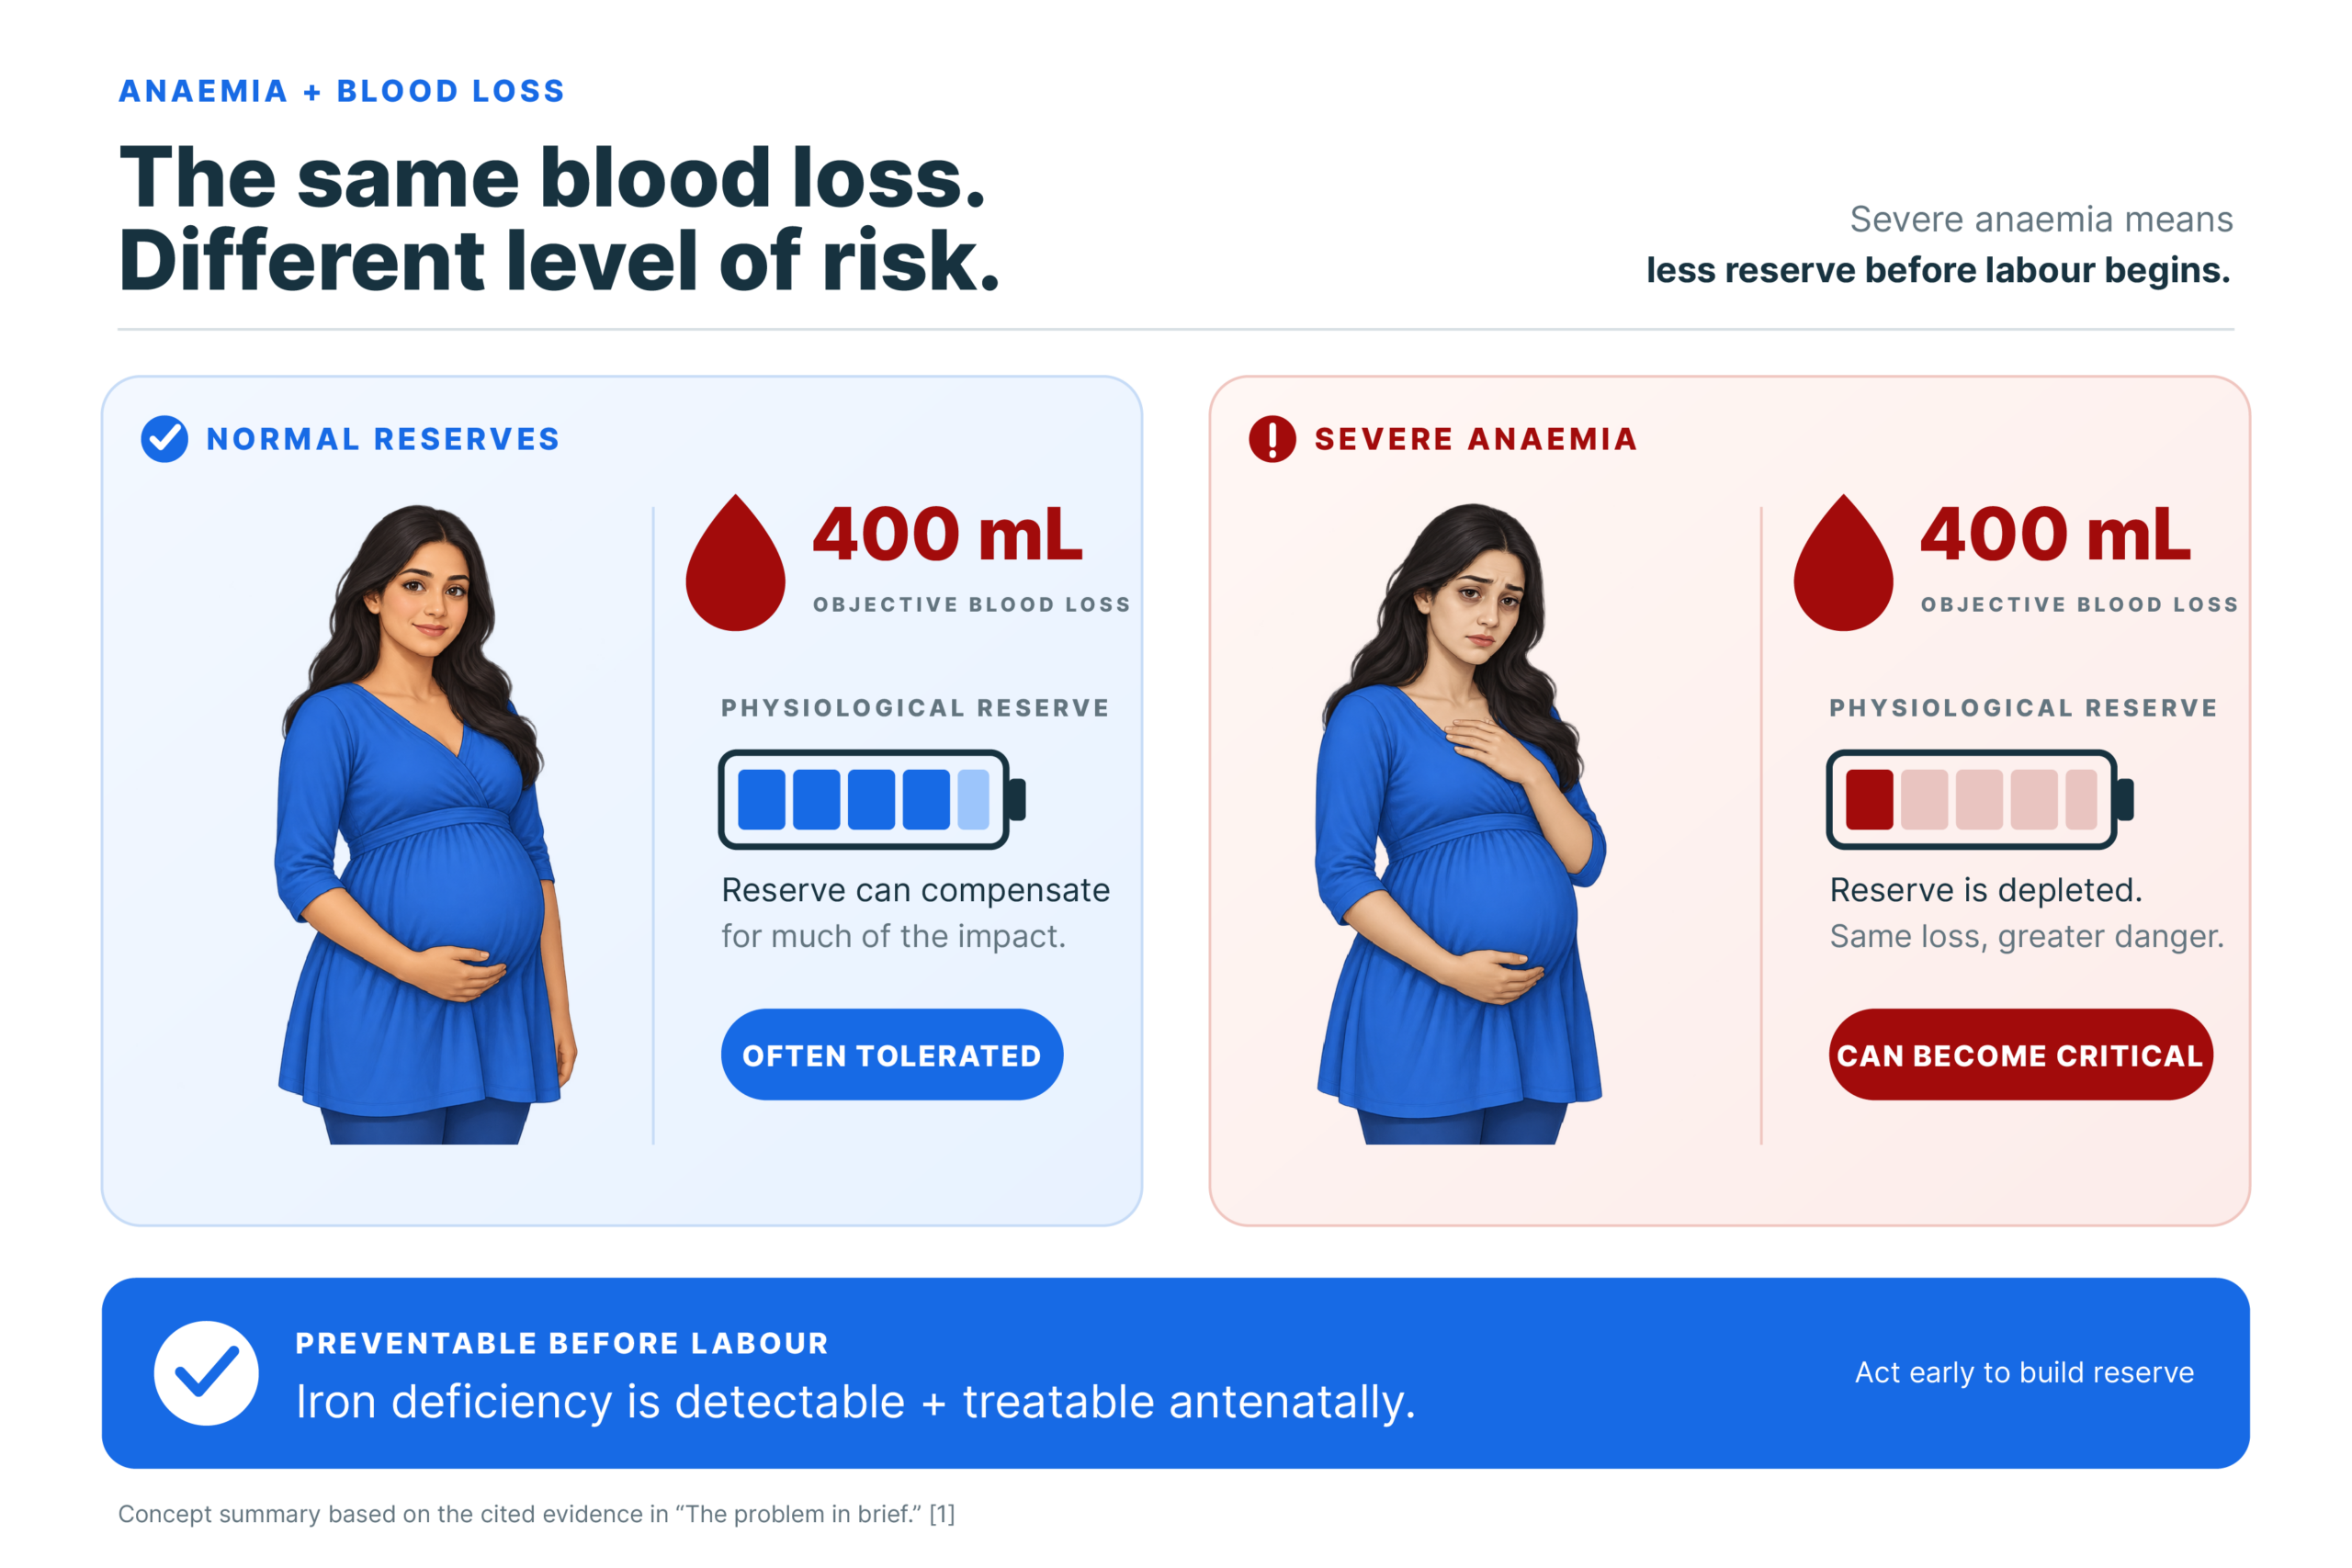
Anaemia influences a woman’s ability to withstand blood loss. This could be due to compensatory increases in cardiac output, placental size and vascularity; reductions in the oxygen carrying capacity of blood, compromising myometrial contractility; and impaired blood clotting [1]. In addition to this, a woman in labour with severe anaemia already starts with diminished reserves. As a result: the average 400 mL blood loss tolerated by a woman with normal reserves can become critical for a woman with severe anaemia.
Most pregnancy-related anaemia is due to iron deficiency, which is detectable and treatable well before labour, making the risks above preventable [1]. This page elaborates how anaemia can be prevented antenatally.
The anaemia loop
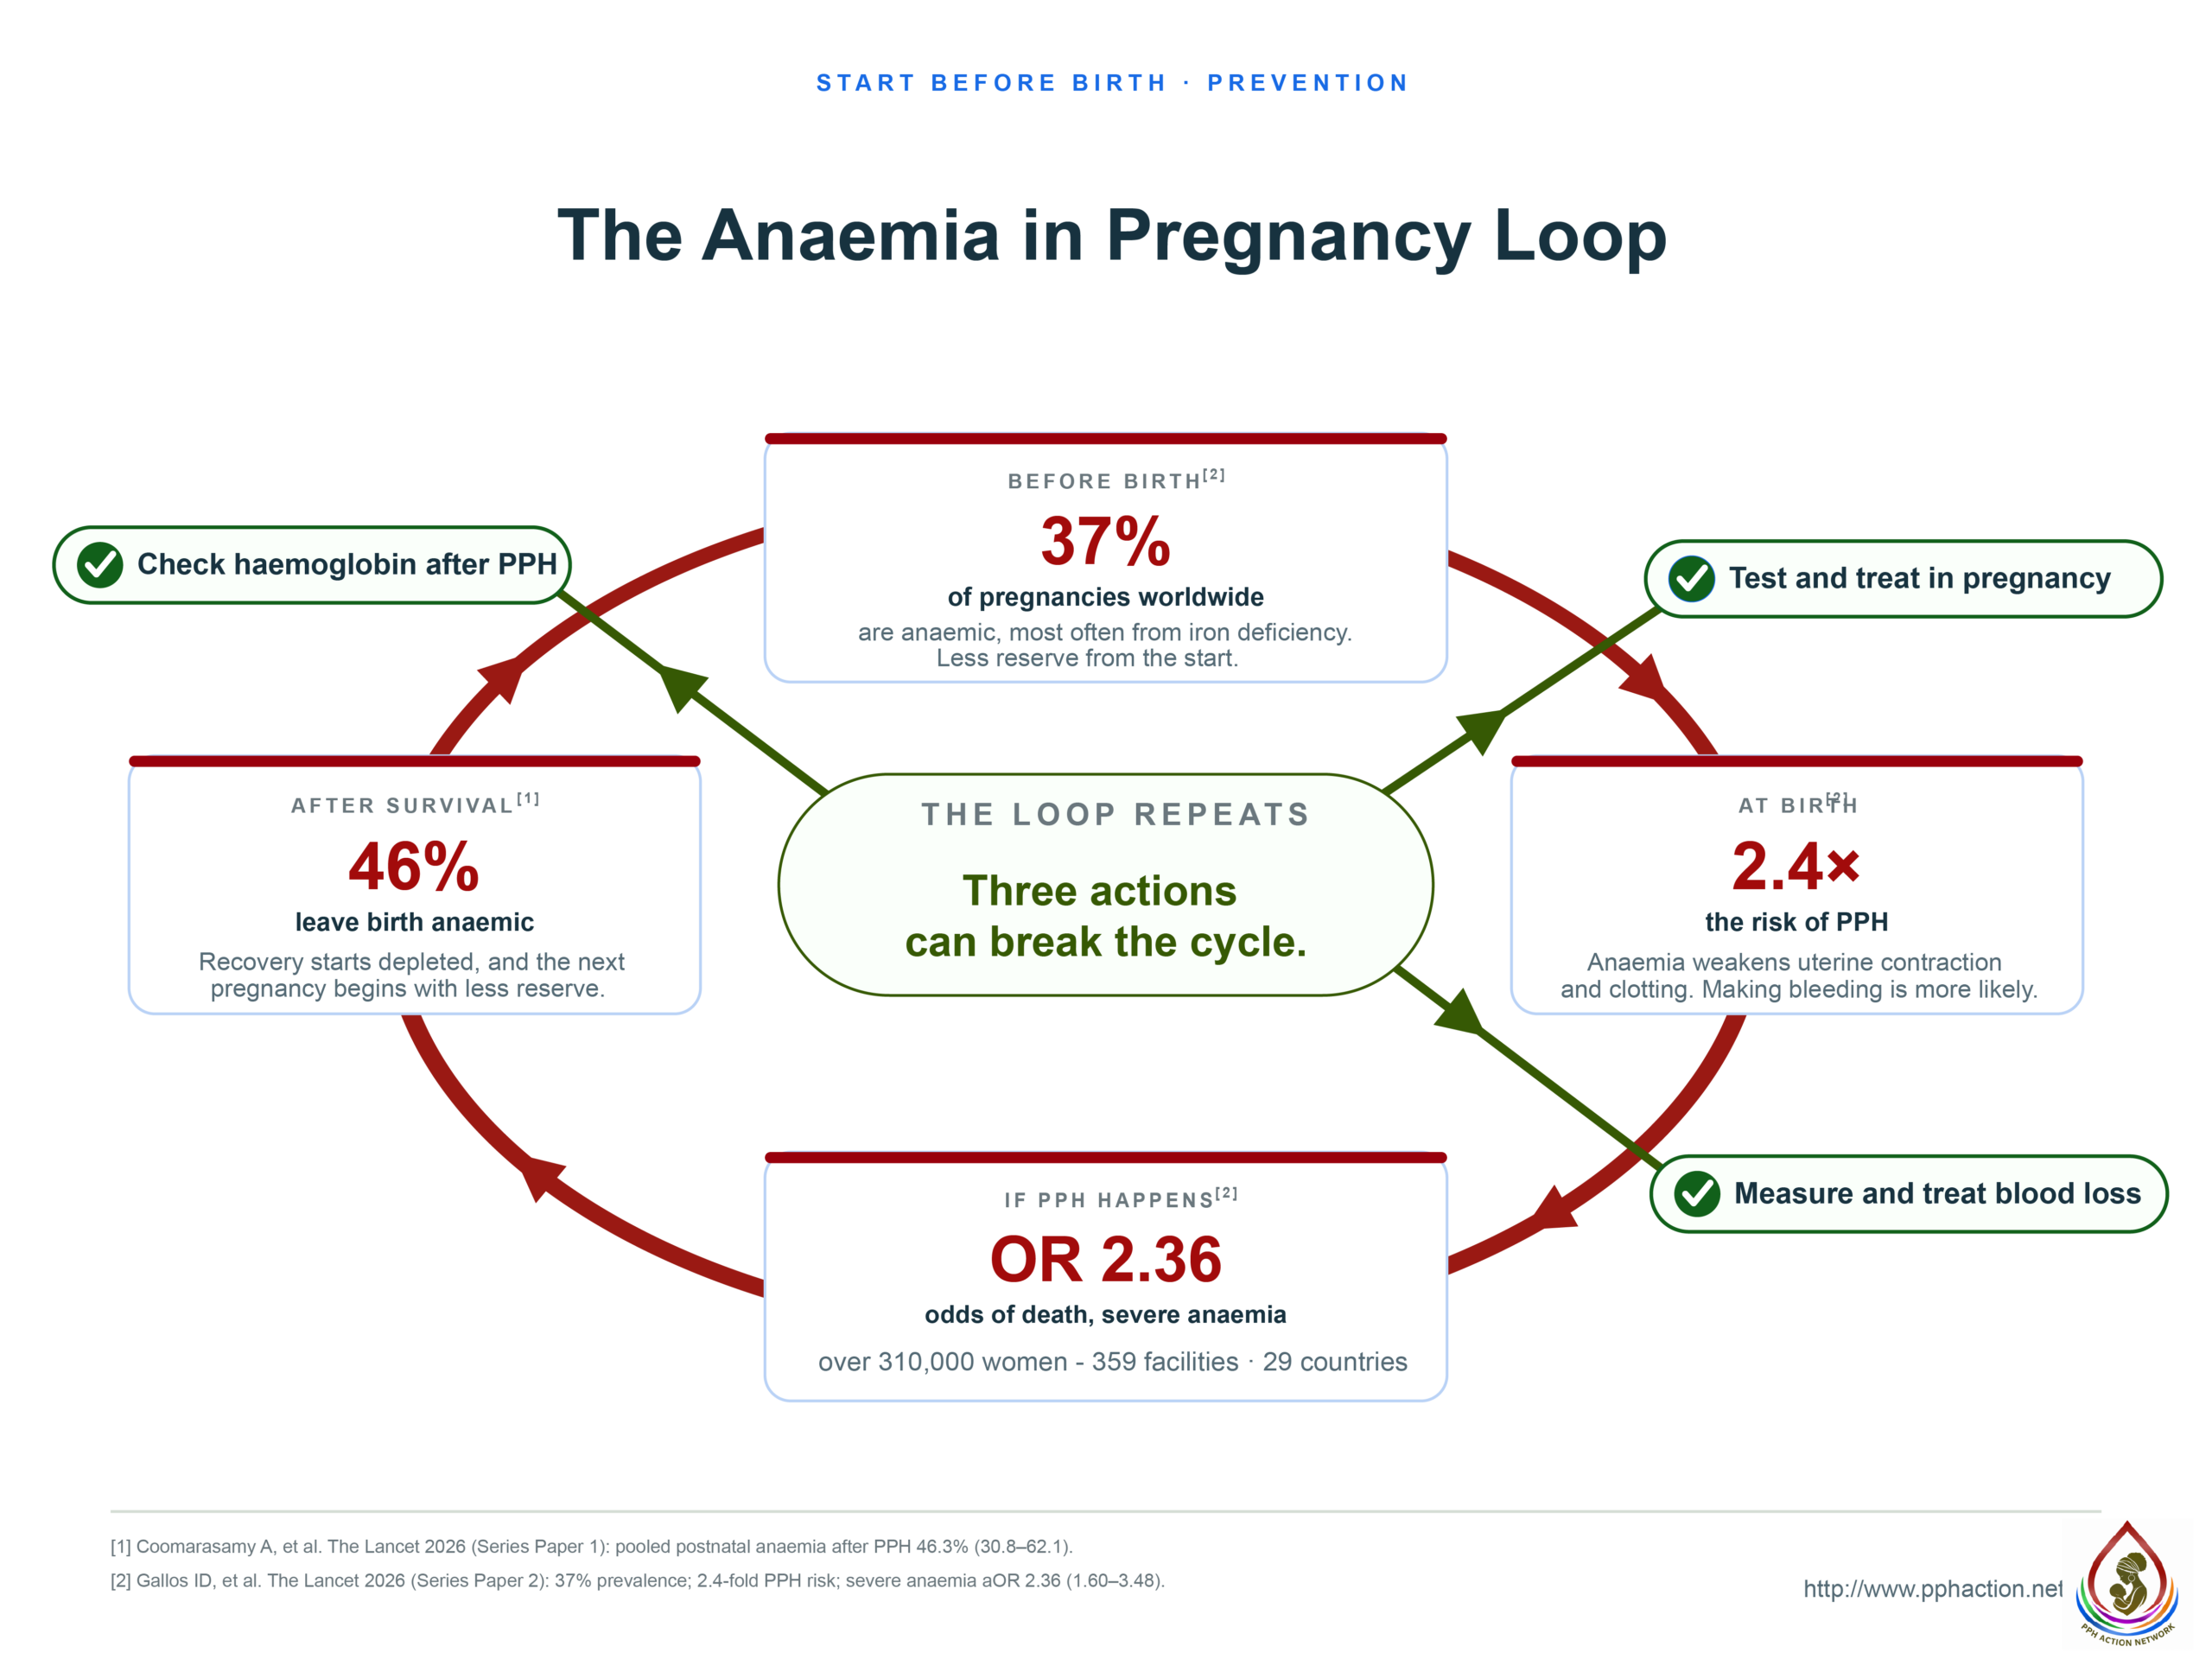
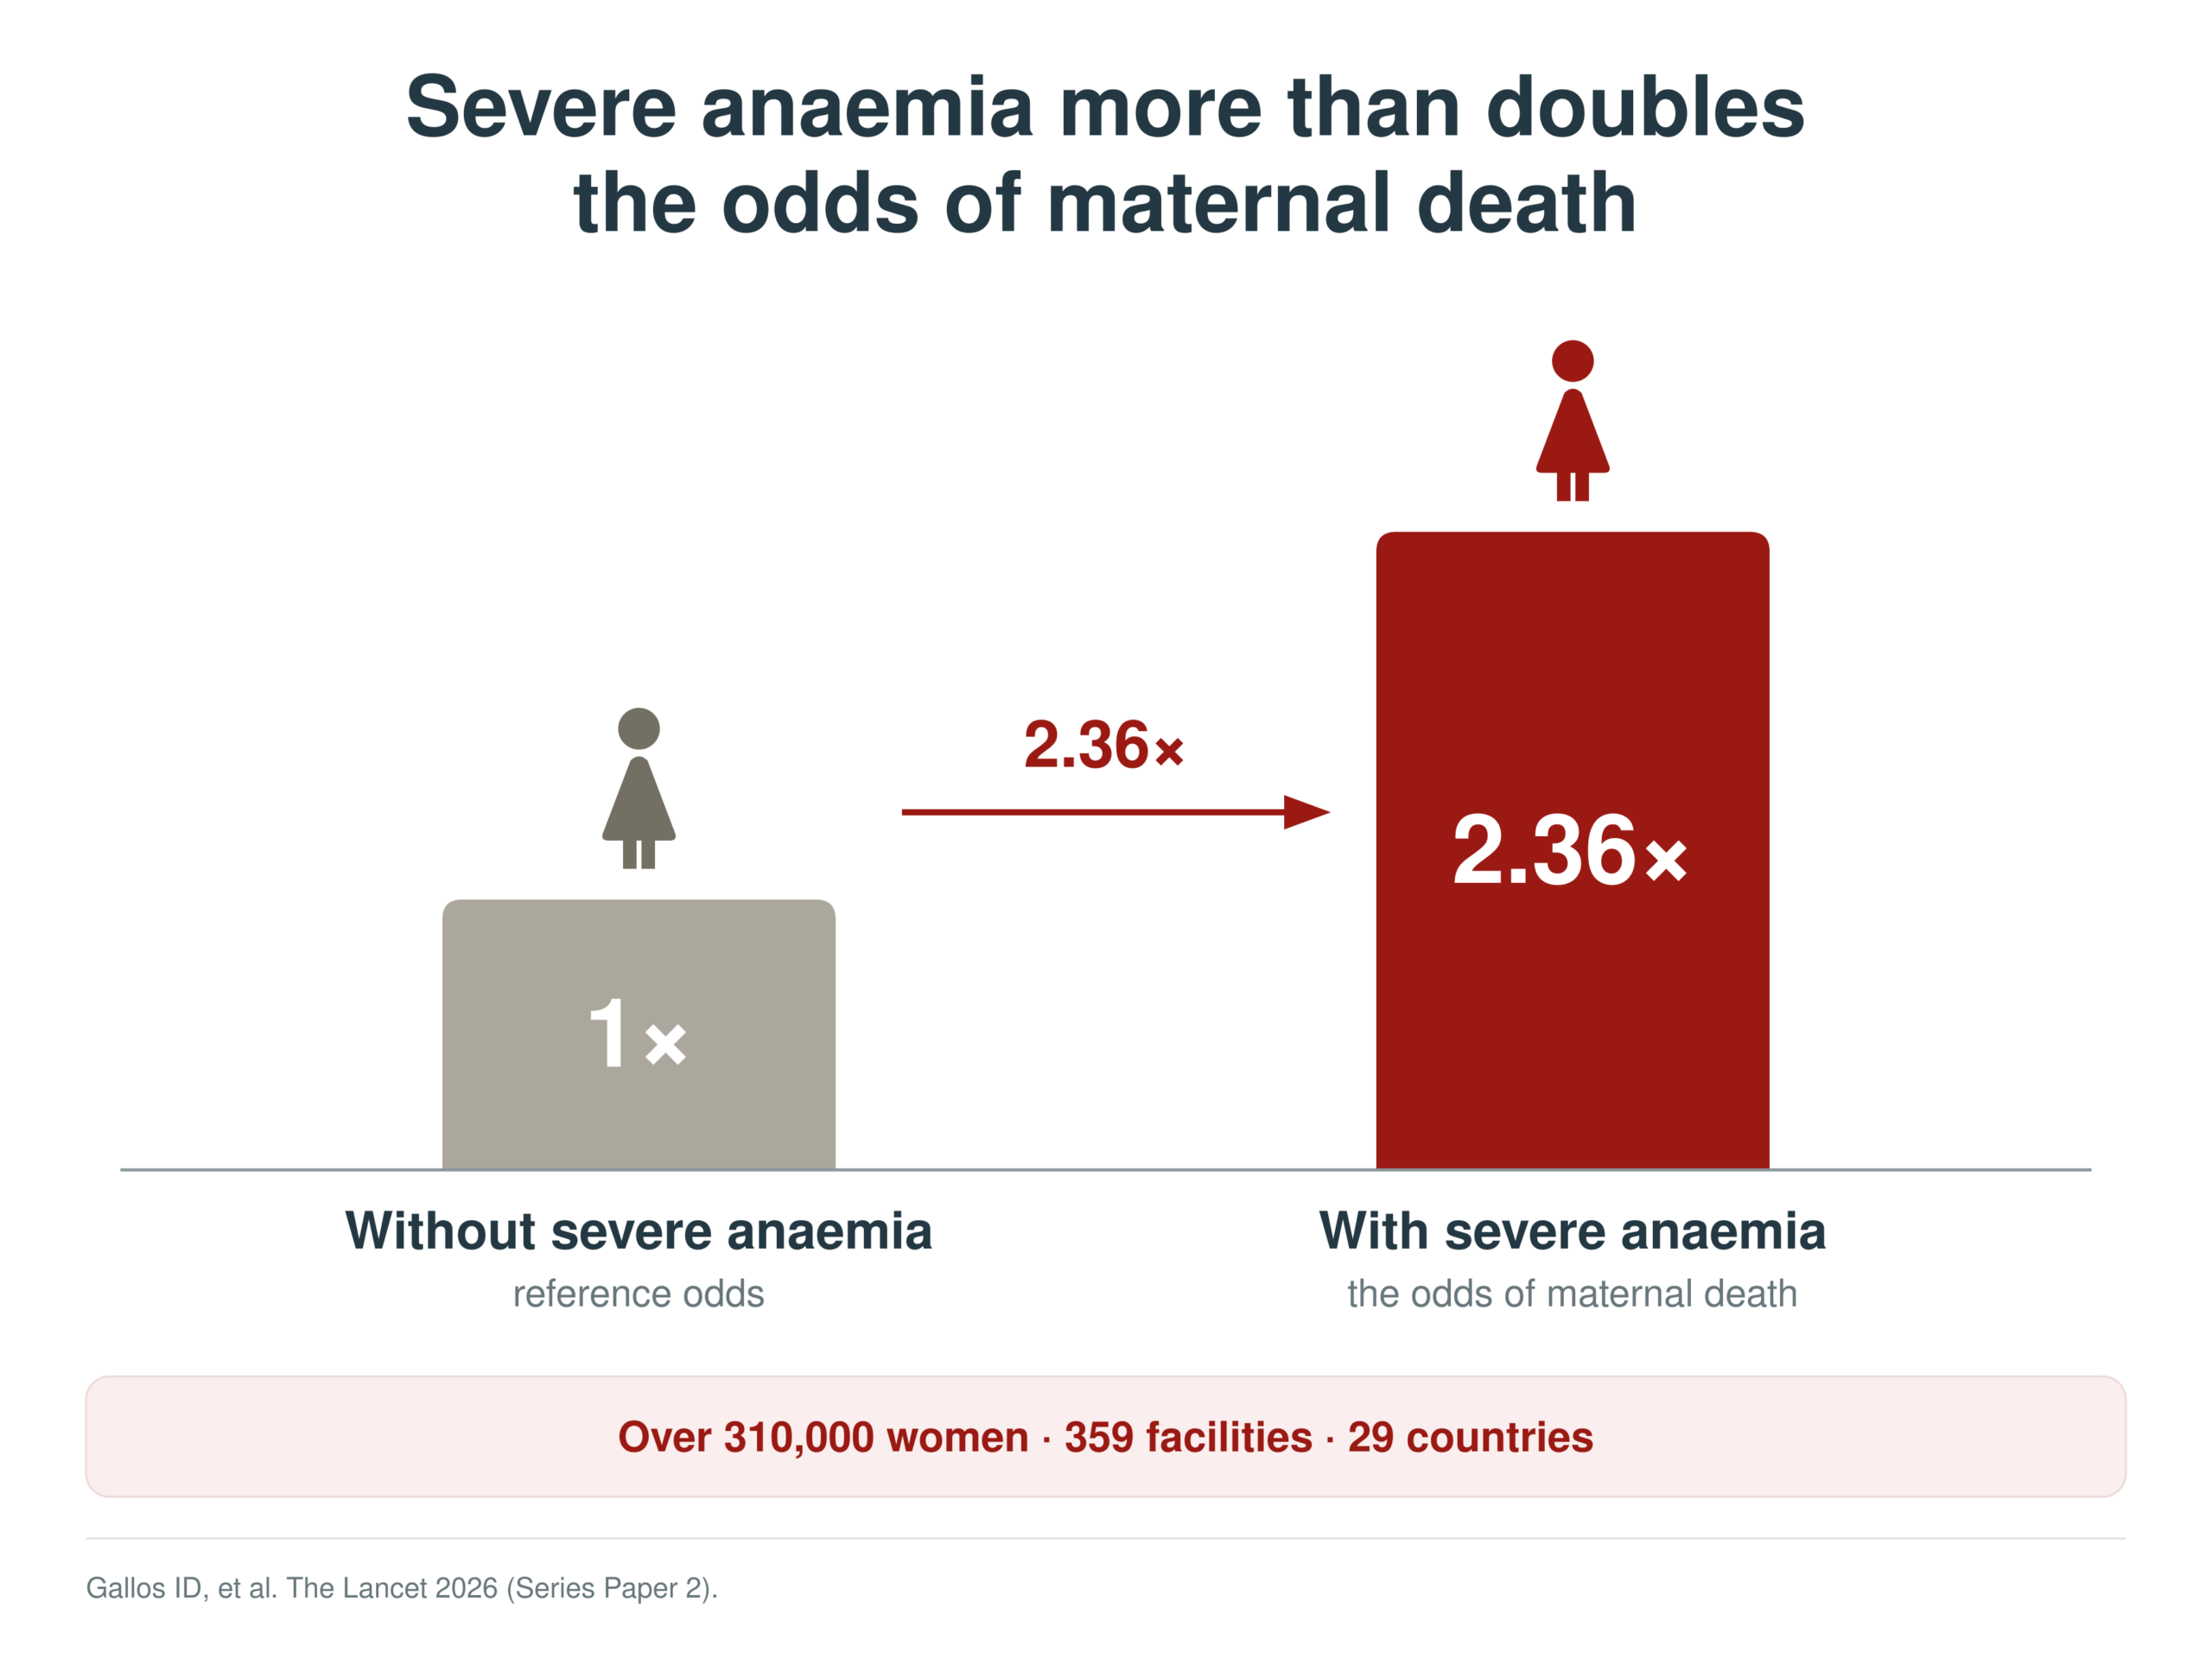
Anaemia increases the risks and effects of postpartum haemorrhage: women with anaemia face a 2.4-fold higher risk of death [1] [4] [5]. For survivors, the relationship does not end there; severe anaemia delays recovery and compounds the risk of future pregnancies [2]. Left unaddressed, the cycle continues throughout a woman’s reproductive life.
A strategic opportunity
Among all risk factors for postpartum haemorrhage, anaemia holds a key place in guidelines as it can be easily identified and managed at low cost. Detection involves measuring haemoglobin, and treatments for anaemia can include:

For policymakers
The consequences of leaving anaemia untreated reach beyond the woman herself, potentially reducing her capacity to work and care for her children [1].
Detecting and treating anaemia is therefore a strong choice for a ministry deciding where its maternal health budget should be directed.
Offer contraception
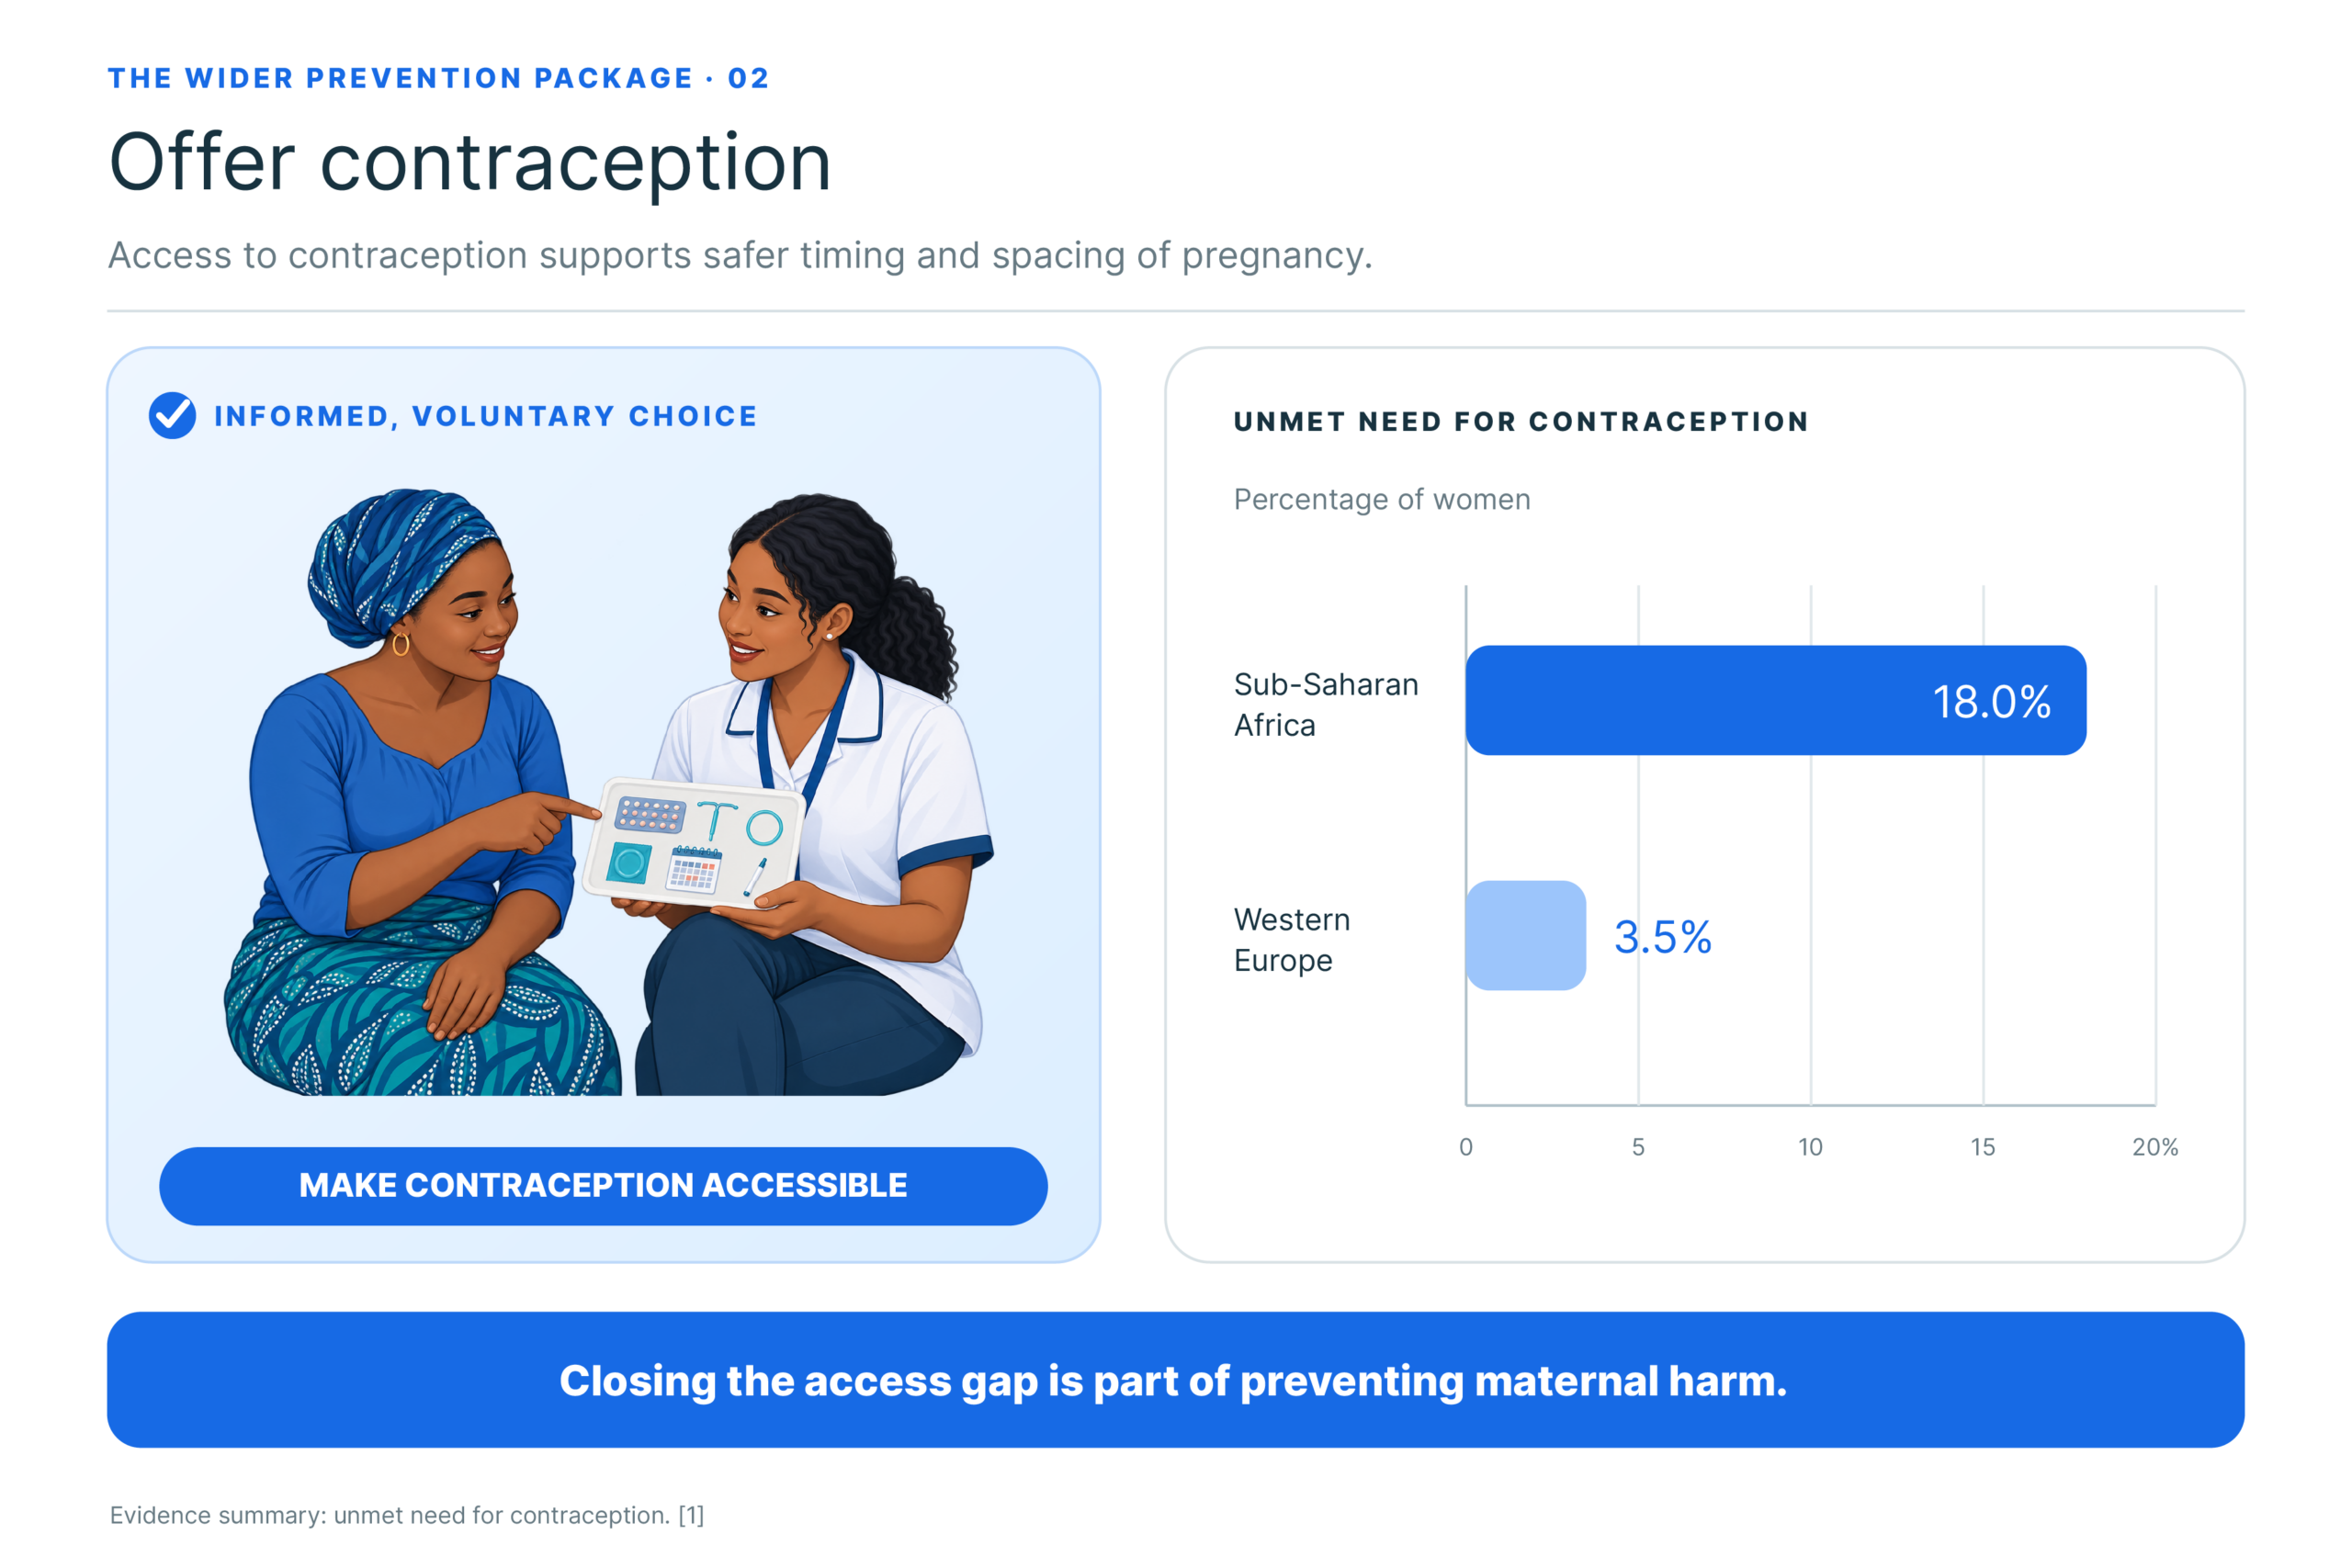
18.0% of women in sub-Saharan Africa face an unmet need for contraception, compared to only 3.5% in western Europe [1].
Avoiding unnecessary caesarean sections
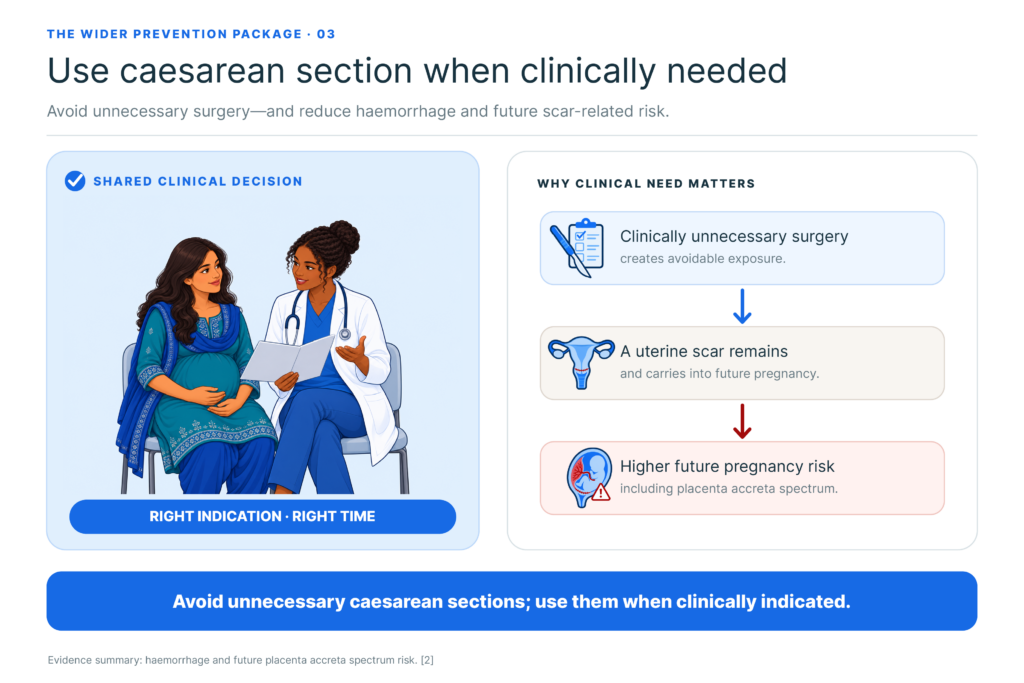
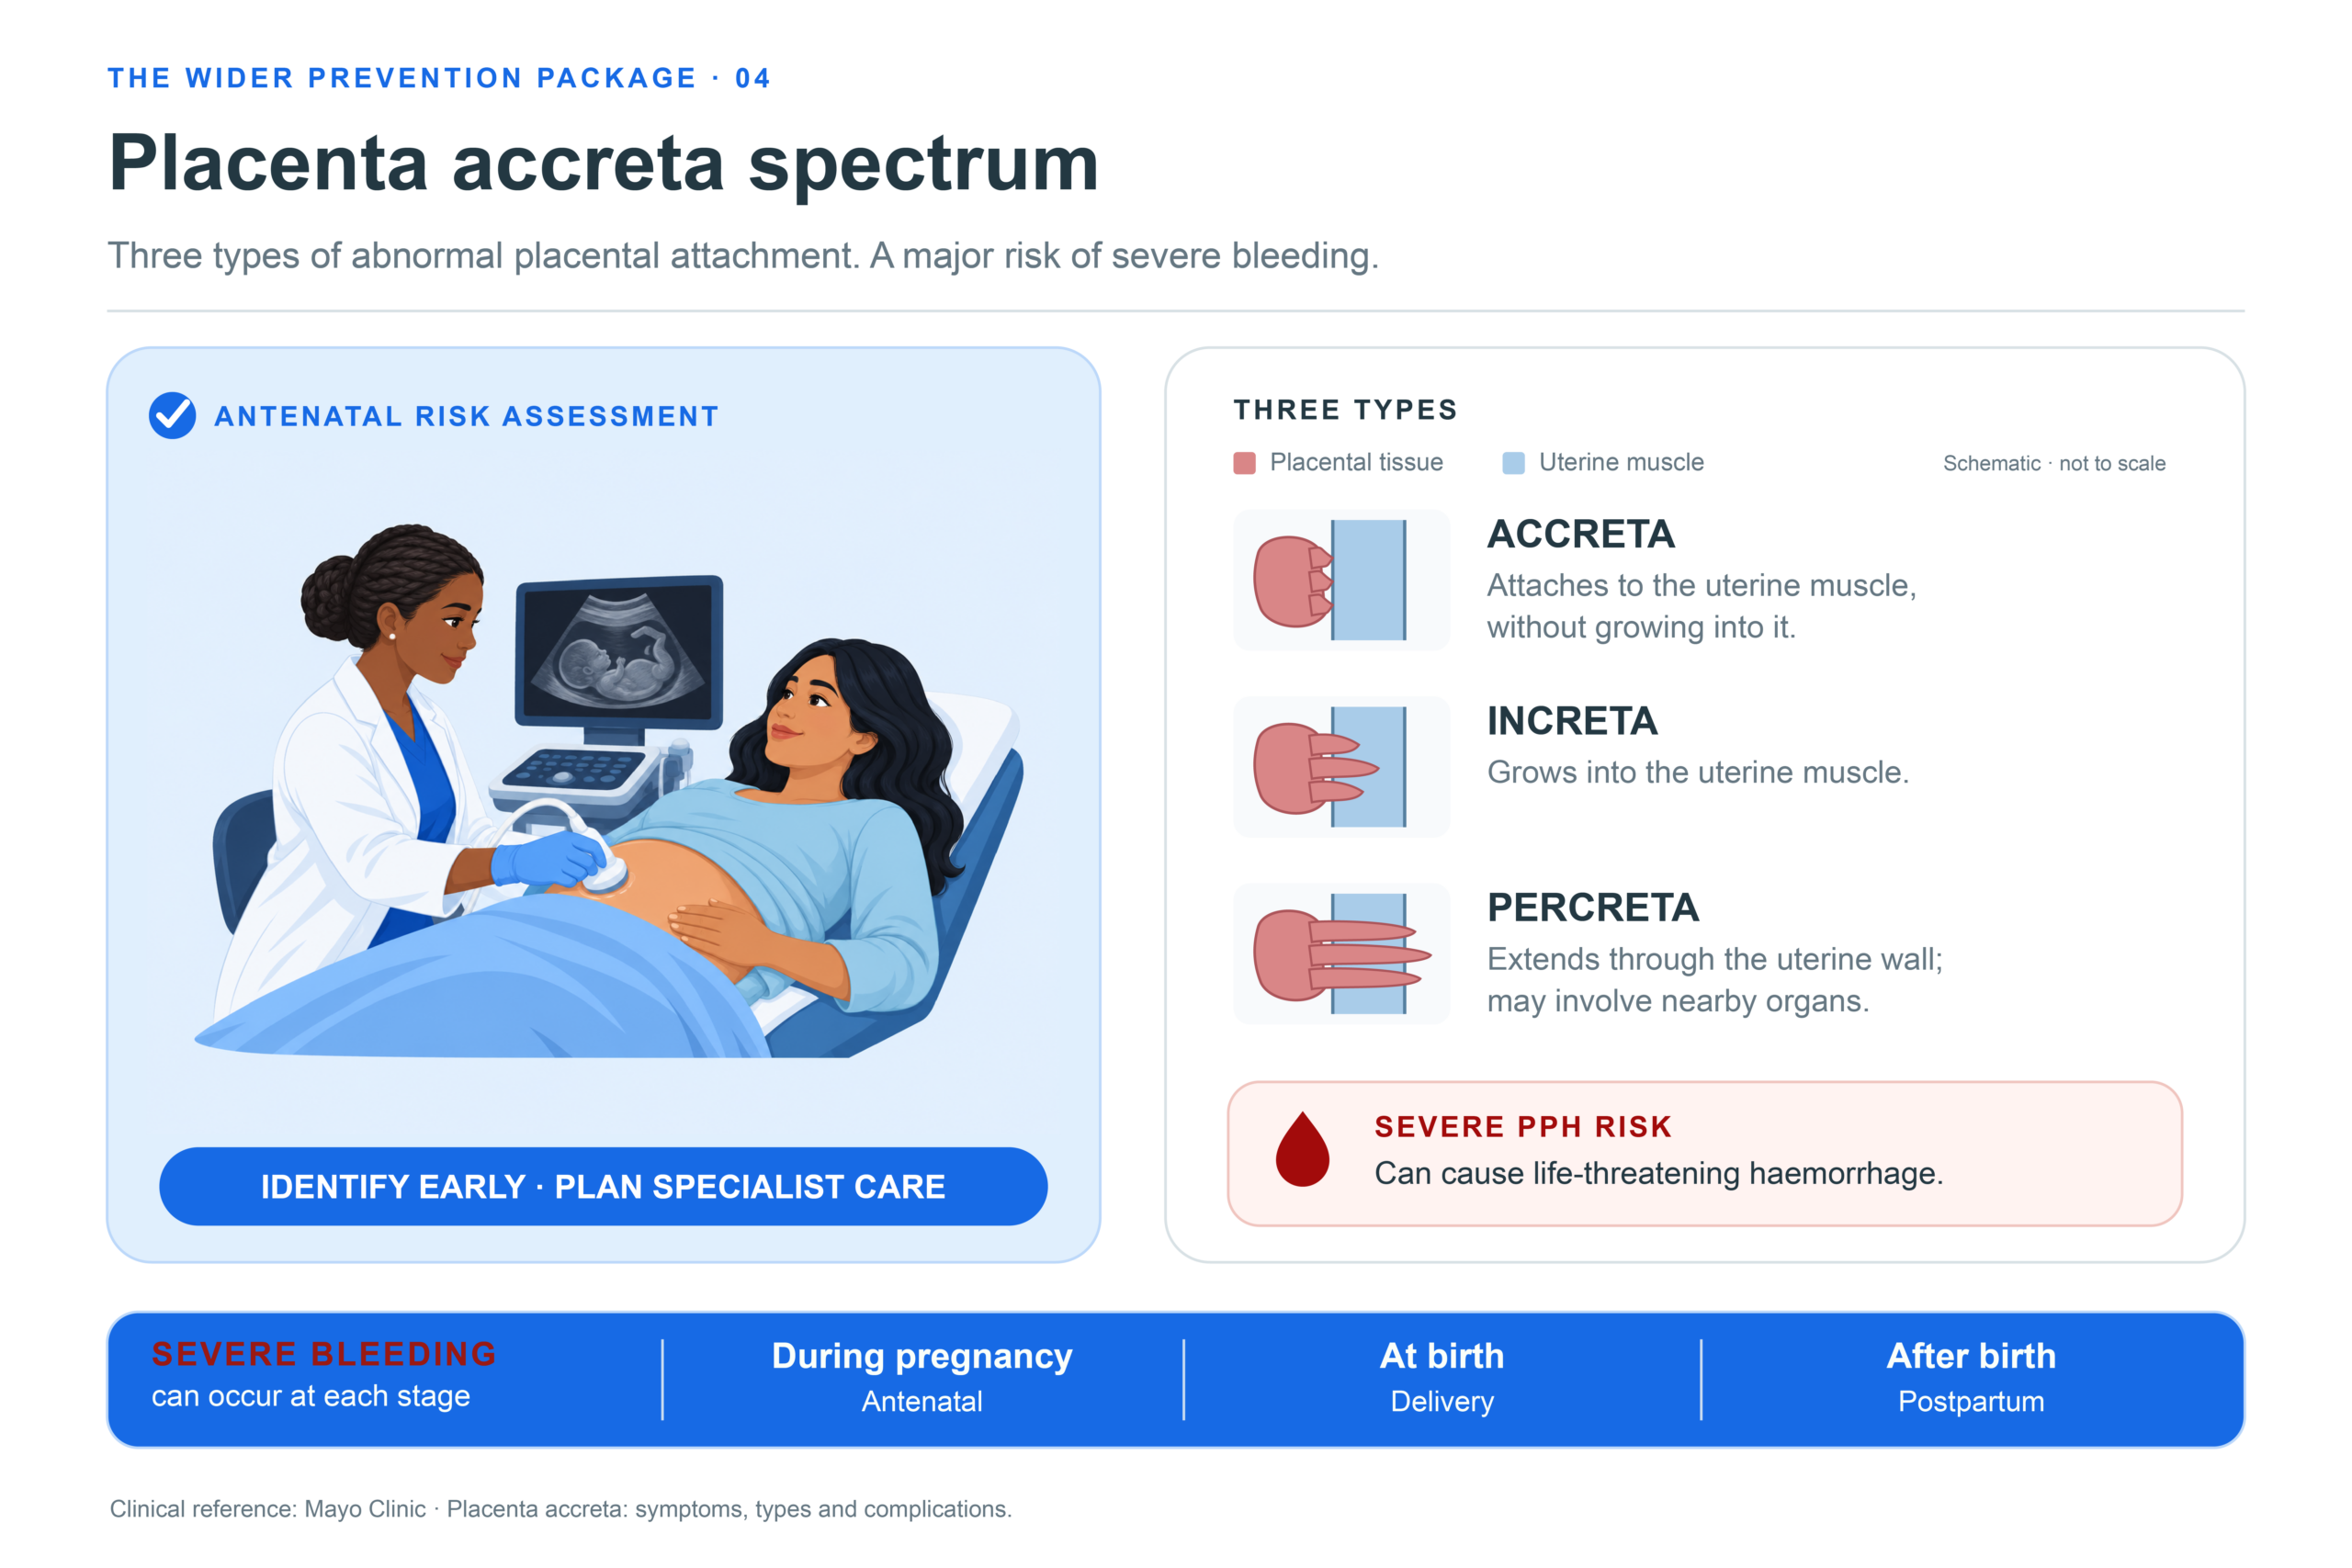
As well as increasing the risk of haemorrhage, caesarean sections increase the risk in future pregnancies of placenta accreta spectrum (abnormal placenta location) [2].
The bridge
When prevention isn’t sufficient
Postpartum haemorrhage can still happen in some women despite anaemia being detected and treated. When it occurs, survival depends on what happens in the critical minutes that follow: how quickly the initial response is started and, how rapidly the situation is escalated.
References
[1] Gallos ID, Sindhu KN, Yunas I, et al. Prevention of postpartum haemorrhage: from evidence to implementation at scale. The Lancet, 2026. Paper · DOI
[2] Coomarasamy A, Sindhu KN, Gallos I, et al. Postpartum haemorrhage: epidemiology, consequences, and missed opportunities. The Lancet, 2026. Paper · DOI
[3] WHO, FIGO, ICM. Consolidated guidelines for the prevention, diagnosis and treatment of postpartum haemorrhage, 2025. Paper

